

Psychiatric medication plays an important role in the treatment of many mental health conditions, including depression, anxiety disorders, obsessive-compulsive disorder (OCD), bipolar disorder, schizophrenia and attention-deficit/hyperactivity disorder (ADHD).
These medications, also known as psychotropic drugs, influence processes in the brain involved in mood, thinking, attention, emotional regulation and behaviour. When prescribed appropriately, they can relieve symptoms, improve everyday functioning and reduce the risk of future episodes of illness.
At CHMC German Clinic for Psychiatry and Psychology in Dubai, psychiatric medication is prescribed as part of an individualised treatment approach that may also include psychotherapy. This article explains the main types of psychiatric medication, how they work, when they are used and what patients should know about treatment safety.
For Psychiatric Assessment and Treatment Contact Our Consultant Psychiatrist:
How Does Psychiatric Medication Work?
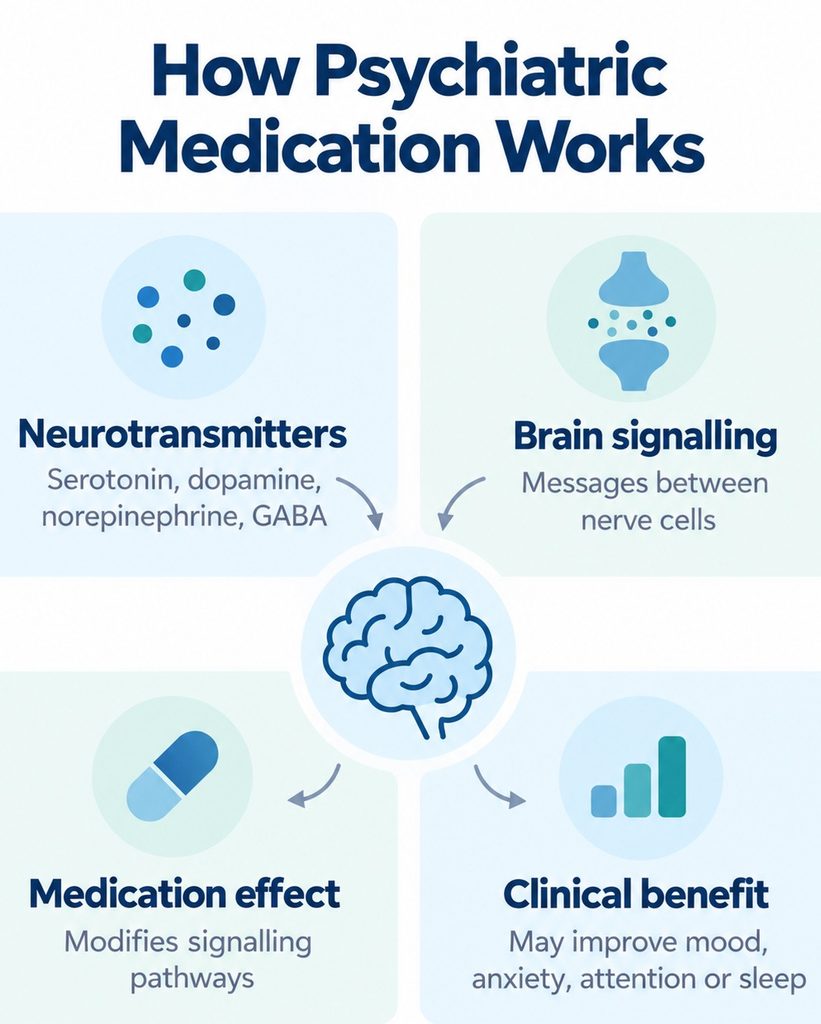
Psychiatric medications act on biological systems involved in communication between nerve cells. Many influence neurotransmitters, chemical messengers that help regulate mood, motivation, attention, sleep and other brain functions. Important neurotransmitters include serotonin, dopamine, norepinephrine, gamma-aminobutyric acid (GABA) and glutamate.
Different medications affect these systems through different mechanisms. For example, many antidepressants influence serotonin or norepinephrine signalling, while antipsychotics primarily act on dopamine receptors and, in many cases, serotonin receptors. Benzodiazepines enhance the inhibitory effects of GABA, whereas stimulant medications used for ADHD influence dopamine and norepinephrine activity in brain networks involved in attention and behavioural control.
Although psychiatric medications modify neurotransmitter signalling, mental disorders cannot generally be explained by a simple chemical imbalance. Depression, anxiety and other psychiatric conditions develop through complex interactions between biological vulnerability, psychological processes and environmental influences. The effectiveness of medication therefore does not establish that a particular neurotransmitter deficiency caused the disorder.
The therapeutic response also varies between medications and individuals. Some drugs produce noticeable effects within hours, while others require several weeks before substantial improvement becomes apparent. Treatment must therefore be evaluated according to the underlying condition, the medication’s expected onset of action and the patient’s clinical response.
Main Types of Psychiatric Medication
Psychiatric medications are commonly classified according to their principal therapeutic effects and clinical applications. The main groups include antidepressants, antipsychotics, mood stabilizers, anxiolytics, hypnotics, stimulants and medications used in dementia or substance use disorders.
These categories are not completely separate because several medications have more than one psychiatric indication. Certain antidepressants, for example, are effective in both depression and anxiety disorders, while some antipsychotics are also used in bipolar disorder or as additional treatment for depression. Understanding these differences helps explain why psychiatric medication is selected according to the diagnosis rather than individual symptoms alone.

Antidepressants
Antidepressants are widely used in the treatment of depressive disorders and several anxiety-related conditions, including panic disorder and OCD. Their therapeutic purpose is to reduce symptoms and improve functioning, which may involve improvements in mood, motivation, concentration, sleep and participation in everyday activities.
Most antidepressants influence neurotransmitter systems involving serotonin, norepinephrine or both. Although their effects on neurotransmitter signalling begin relatively soon after administration, meaningful improvement in depression usually develops over several weeks. The delayed therapeutic response is thought to involve adaptive changes in neuronal signalling and brain networks rather than a simple immediate increase in neurotransmitter concentrations.
The choice of antidepressant depends on the patient’s symptoms, previous treatment response, coexisting medical or psychiatric conditions and potential side effects. Differences in the way these medications affect sleep, appetite, energy and other functions can be relevant when selecting treatment.
Selective Serotonin Reuptake Inhibitors (SSRIs)
SSRIs are among the most frequently prescribed antidepressants and are commonly considered first-line pharmacological treatments for depression and several anxiety disorders. They inhibit serotonin reuptake, increasing the availability of serotonin for communication between nerve cells. Examples include sertraline, escitalopram, fluoxetine, fluvoxamine, paroxetine and citalopram.
SSRIs are generally better tolerated than older tricyclic antidepressants, although they can still cause significant side effects. Common adverse effects include nausea, gastrointestinal disturbances, sleep difficulties, restlessness and sexual dysfunction. The likelihood and severity of these effects vary between individual medications and patients.
Serotonin-Norepinephrine Reuptake Inhibitors (SNRIs)
SNRIs affect both serotonin and norepinephrine signalling and are used to treat depression and selected anxiety disorders. Examples include venlafaxine, desvenlafaxine and duloxetine. Some medications in this group, particularly duloxetine, are also used for certain chronic pain conditions.
Their side-effect profile overlaps with that of SSRIs, although sweating, changes in blood pressure and discontinuation symptoms may require particular attention with certain SNRIs. The choice between an SSRI and an SNRI depends on the patient’s clinical presentation, previous medication response and individual tolerability.
Tricyclic Antidepressants (TCAs)
Tricyclic antidepressants are an older but still clinically valuable group that includes amitriptyline, nortriptyline, imipramine and clomipramine. In addition to depression, selected medications are used for neuropathic pain and OCD. Clomipramine, for example, has established efficacy in OCD, although tolerability and safety considerations often favour SSRIs as the initial pharmacological treatment.
Tricyclic antidepressants may cause dry mouth, constipation, urinary difficulties, sedation and blood pressure changes. Some can also affect cardiac conduction and are particularly dangerous in overdose. Consequently, they are generally not the preferred first-line treatment for many patients with depression.
Other Antidepressants
Several antidepressants have mechanisms of action that differ from those of SSRIs, SNRIs and tricyclic antidepressants. Mirtazapine influences noradrenergic and serotonergic receptor systems and may be particularly useful when depression is accompanied by insomnia or reduced appetite. Bupropion primarily affects norepinephrine and dopamine signalling and has a different side-effect profile from serotonergic antidepressants, while vortioxetine combines serotonin transporter inhibition with activity at several serotonin receptors.
Monoamine oxidase inhibitors (MAOIs), including moclobemide, provide additional treatment options in selected circumstances. However, their use requires attention to potential drug interactions and other prescribing precautions. Rather than classifying antidepressants simply as stimulating or sedating, treatment selection should consider their complete pharmacological profile and the patient’s individual needs.
Side Effects and Duration of Antidepressant Treatment
Antidepressant side effects often emerge during the first days or weeks of treatment and may diminish as treatment continues. However, persistent adverse effects, including sexual dysfunction or emotional blunting, can affect quality of life and should be discussed with the prescribing psychiatrist. Particular attention is also necessary when treatment begins or doses change, especially in younger patients who may experience worsening agitation or suicidal thoughts.
Antidepressants do not generally cause addiction in the same way as benzodiazepines or substances with reinforcing intoxicating effects. Nevertheless, abrupt discontinuation can produce withdrawal symptoms such as dizziness, nausea, insomnia, anxiety and unusual sensory experiences. Treatment should therefore usually be reduced gradually, with the pace of discontinuation adapted to the medication and the patient’s response.
The appropriate duration of antidepressant treatment depends on the severity and course of the disorder. Following remission from depression, medication is generally continued for a period to reduce the risk of relapse, while recurrent or chronic depression may require longer-term treatment.
For more detailed information, see our articles on antidepressant medication and the treatment of depression in Dubai.
Antipsychotic Medication
Antipsychotics are primarily used to treat disorders involving psychotic symptoms, including hallucinations, delusions and severely disorganised thinking. They are essential in the treatment of schizophrenia and other psychotic disorders, but their applications extend beyond psychosis. Certain antipsychotics are also effective in acute mania, bipolar disorder and, in selected circumstances, depression that has not responded adequately to conventional treatment.
Most antipsychotic medications influence dopamine signalling, particularly through dopamine D2 receptors. Many also act on serotonin and other neurotransmitter systems, producing differences in their therapeutic effects and side-effect profiles. Some medications primarily block dopamine receptors, whereas others, such as aripiprazole, act as partial dopamine agonists. These pharmacological differences contribute to the selection of individual medications for particular clinical situations.
First-Generation and Second-Generation Antipsychotics
Antipsychotics are commonly divided into first-generation and second-generation medications. First-generation antipsychotics, such as haloperidol, are effective against psychotic symptoms but are generally associated with a greater risk of certain movement-related adverse effects, including muscle stiffness, tremor and akathisia.
Second-generation antipsychotics include risperidone, olanzapine, quetiapine, aripiprazole, clozapine and ziprasidone. Although these medications are sometimes described collectively as having fewer neurological side effects, their individual risk profiles differ considerably. Olanzapine, for example, is associated with substantial metabolic risks, while aripiprazole may cause akathisia. Risperidone can cause movement-related adverse effects and increased prolactin levels, particularly at higher doses.
Clozapine has a specific role in treatment-resistant schizophrenia and may be effective when other antipsychotics have failed. However, its potential for serious adverse effects requires specialised monitoring, including regular blood investigations.
Side Effects and Monitoring of Antipsychotic Treatment
Potential adverse effects of antipsychotic medication include sedation, weight gain, metabolic disturbances, increased prolactin levels and movement disorders. Prolonged exposure to some antipsychotics may also lead to tardive dyskinesia, a potentially persistent condition characterised by involuntary movements.
Because these risks vary between medications, treatment should be monitored according to the patient’s clinical condition and the drug’s specific properties. Depending on the medication, monitoring may include body weight, blood pressure, glucose and lipid measurements, assessment of movement symptoms and an ECG when indicated.
Long-term antipsychotic treatment may be necessary to prevent recurrence of psychotic illness. However, the continued need for medication, its effectiveness and potential adverse effects should be reviewed periodically rather than assuming that the original treatment regimen will remain appropriate indefinitely.
For more information, visit our article on psychotic disorders and their treatment.
Mood Stabilizers
Mood stabilizers are medications used primarily in the treatment of bipolar disorder, which is characterised by episodes of depression, mania or hypomania. Their principal purpose is to treat acute mood episodes and reduce the risk of future recurrence, although individual medications differ in their effectiveness across the phases of the illness.
Some mood stabilizers are particularly effective in treating mania, while others are more useful for preventing depressive episodes. Treatment selection must therefore consider whether the immediate objective is to control an acute episode or maintain long-term mood stability. Lithium, certain anticonvulsants and selected second-generation antipsychotics have established roles in bipolar disorder treatment.
Lithium
Lithium is one of the most extensively studied and effective medications for bipolar disorder. It is used in the treatment of acute mania and in long-term relapse prevention, with evidence supporting protective effects against both manic and depressive episodes. Research also suggests that lithium may reduce suicidal behaviour in patients with mood disorders, although estimates of this benefit vary between studies.
Despite its long clinical history, lithium’s precise mechanism of action is not completely understood. It influences several intracellular signalling processes involved in neuronal function, but its clinical effectiveness cannot be attributed to a single neurotransmitter mechanism.
Lithium treatment requires individual dose adjustment and regular monitoring because its therapeutic blood concentration is relatively close to potentially toxic levels. Kidney function, thyroid function, calcium levels and serum lithium concentrations must be assessed at appropriate intervals. Dehydration, changes in fluid or sodium balance, impaired kidney function and interactions with certain medications can increase the risk of toxicity.
Symptoms such as marked tremor, vomiting, diarrhoea, confusion, muscle weakness or impaired coordination may indicate lithium toxicity and require urgent medical assessment. Patients receiving lithium should also receive clear guidance about hydration, medication interactions and the importance of maintaining stable treatment.
Anticonvulsants Used as Mood Stabilizers
Several medications originally developed for epilepsy also have established applications in bipolar disorder. Lamotrigine is particularly valuable in maintenance treatment, especially for preventing depressive episodes, but it is not effective for acute mania. Because rapid dose escalation increases the risk of serious skin reactions, lamotrigine must be introduced gradually according to an appropriate titration schedule.
Valproate is effective in acute mania and may be used for maintenance treatment in selected patients. However, it carries significant reproductive risks, including fetal malformations and neurodevelopmental harm following exposure during pregnancy. Its use therefore requires strict safety precautions, particularly in people of reproductive potential.
Carbamazepine provides another option in selected cases, although its potential for drug interactions and adverse effects can complicate treatment. Liver function, blood counts and other relevant parameters may require monitoring, depending on the medication and the patient’s circumstances.
Mood stabilizers are often continued over extended periods because bipolar disorder commonly follows a recurrent course. Decisions about long-term treatment should consider the type and frequency of previous episodes, response to medication, adverse effects and risk of relapse.
For further information, see mood stabilizers in bipolar disorder and our article on bipolar disorder treatment.
Anxiolytics and Hypnotics
Anxiolytics are medications used to reduce anxiety, while hypnotics are intended to promote sleep. Some medications have both effects, but they differ substantially in their mechanisms, appropriate duration of use and potential risks. The choice of treatment depends on whether anxiety or insomnia is temporary, associated with an acute psychiatric condition or part of a persistent disorder requiring longer-term management.
Benzodiazepines
Benzodiazepines include lorazepam, diazepam, clonazepam, oxazepam and bromazepam. They enhance the inhibitory effects of GABA, producing anxiolytic, sedative and muscle-relaxing effects. Certain benzodiazepines also have anticonvulsant properties.
These medications can provide relatively rapid relief of severe anxiety, agitation or acute insomnia. However, their use is generally restricted to short-term treatment or specific clinical indications because tolerance, physical dependence and withdrawal symptoms can develop with repeated use. Their potential for dependence must be distinguished from their therapeutic effectiveness in carefully selected situations.
Common adverse effects include drowsiness, impaired concentration, reduced coordination and slower reaction times. Combining benzodiazepines with alcohol, opioids or other sedating substances can cause dangerous respiratory depression. Abrupt discontinuation after regular use may produce severe withdrawal symptoms, including marked anxiety, insomnia and occasionally seizures, making medically supervised tapering essential when dependence has developed.
Non-Benzodiazepine Hypnotics
Non-benzodiazepine hypnotics, commonly known as Z-drugs, include zolpidem, zopiclone and zaleplon. Although structurally different from benzodiazepines, they act on related GABA receptor systems and share some of their risks.
These medications may be prescribed for short-term insomnia treatment in selected patients, but prolonged use is generally discouraged because of tolerance, dependence and withdrawal concerns. They can also impair next-day alertness and occasionally cause complex sleep-related behaviours, such as walking or performing activities without full awareness.
For chronic insomnia, cognitive behavioural therapy for insomnia (CBT-I) is generally recommended as the first-line treatment. When insomnia occurs alongside depression, anxiety or another psychiatric condition, the underlying disorder should also be addressed rather than relying exclusively on sleeping medication.
Medication for Long-Term Anxiety Treatment
Benzodiazepines are usually not the preferred long-term pharmacological treatment for anxiety disorders. Depending on the diagnosis, antidepressants such as SSRIs or SNRIs may provide a more appropriate option, while psychotherapy, particularly cognitive behavioural therapy, is another established treatment approach.
The decision to use medication, psychotherapy or both depends on symptom severity, previous treatment response and patient preferences. For further information, see our anxiety treatment page.
Stimulant Medication for ADHD
Stimulant medications are among the most effective pharmacological treatments for ADHD. They influence dopamine and norepinephrine signalling in brain networks responsible for attention regulation, behavioural inhibition and executive functioning. Their therapeutic purpose is not simply to increase energy but to improve sustained attention, reduce impulsivity and support everyday functioning.
The main stimulant groups include methylphenidate and amphetamine-based medications, such as lisdexamfetamine. These drugs are available in formulations with different durations of action, allowing treatment to be adapted to the patient’s daily requirements. Depending on the preparation, beneficial effects may become noticeable relatively soon after administration and continue for several hours.
Before stimulant treatment begins, the clinician should review the patient’s psychiatric and medical history, cardiovascular risk factors, pulse, blood pressure and possible contraindications. Common side effects include reduced appetite, insomnia, increased heart rate and elevated blood pressure. An ECG may be indicated when relevant cardiovascular concerns are present, but it is not routinely required for every patient.
Stimulant medications also have misuse and dependence potential, making specialist prescribing and appropriate follow-up important. Non-stimulant medications, including atomoxetine and other selected agents, may provide alternatives when stimulants are unsuitable or insufficiently tolerated.
For detailed information, see ADHD medication in Dubai and ADHD treatment in Dubai.
Medication for Dementia and Cognitive Disorders
Medication used in dementia treatment primarily aims to improve or stabilise cognitive and functional symptoms rather than reverse the underlying neurodegenerative process. The expected benefit depends on the type and severity of dementia, and not every patient responds to treatment.
Acetylcholinesterase inhibitors, including donepezil, rivastigmine and galantamine, reduce the breakdown of acetylcholine, a neurotransmitter involved in learning and memory. They are commonly used in Alzheimer’s disease and may provide modest improvements or temporary stabilisation of cognitive functioning. Some are also used in other dementia syndromes under appropriate clinical circumstances.
Memantine has a different mechanism of action and influences glutamate signalling through NMDA receptors. It is primarily used in moderate to severe Alzheimer’s disease, either alone or in combination with an acetylcholinesterase inhibitor when appropriate.
Potential adverse effects vary between these medications. Acetylcholinesterase inhibitors commonly cause gastrointestinal symptoms and may slow the heart rate, while memantine can cause dizziness, headache or confusion in some patients. Treatment should therefore consider the patient’s medical condition, other medications and overall functional needs.
Although these medications may offer meaningful symptomatic benefits, they do not reliably halt the progression of Alzheimer’s disease. Treatment should be combined with psychosocial support, caregiver education and appropriate planning for the patient’s changing needs.
For more information, see our article on Dementia.
Medication for Alcohol and Substance Use Disorders
Medication can support the treatment of certain substance use disorders, particularly alcohol and opioid use disorders. Its role differs according to the stage of treatment, as some medications help manage acute withdrawal, while others support relapse prevention or long-term recovery.
Alcohol withdrawal may become medically dangerous in patients with severe dependence, especially when there is a history of seizures or delirium. Benzodiazepines are commonly used under medical supervision to prevent or treat serious withdrawal complications, and patients at increased risk may require inpatient management.
Following withdrawal, medications such as acamprosate or naltrexone may help reduce the risk of returning to harmful alcohol use. Acamprosate is primarily used to support abstinence, whereas naltrexone can reduce heavy drinking and alcohol-related reinforcement. Disulfiram provides another option for carefully selected patients by interfering with alcohol metabolism and producing an unpleasant, potentially dangerous reaction when alcohol is consumed.
For opioid use disorder, medications such as buprenorphine or methadone may be used in appropriately authorised treatment settings. These treatments reduce withdrawal symptoms, craving and other risks associated with uncontrolled opioid use.
Pharmacological treatment is most effective when integrated into a broader care plan that addresses psychological, social and medical factors contributing to substance use. Medication selection must also comply with applicable local prescribing regulations.
How Is the Right Psychiatric Medication Selected?
Choosing the appropriate psychiatric medication begins with an accurate diagnosis rather than simply matching an individual symptom to a particular drug. Symptoms such as poor concentration, insomnia, anxiety, irritability and emotional instability can occur in several psychiatric or medical conditions, and their treatment depends on the underlying cause.
For example, concentration difficulties may be associated with ADHD, depression, anxiety disorders or sleep disturbances. Similarly, depressive symptoms can occur in both major depressive disorder and bipolar disorder, although their pharmacological treatment differs considerably. Antidepressant treatment in patients with bipolar disorder requires particular caution because it may contribute to manic or hypomanic switching in some circumstances.
A comprehensive psychiatric assessment therefore considers the nature and development of symptoms, previous episodes of illness, family history, medical conditions, current medications and earlier treatment experiences. Potential contraindications, interactions and individual preferences must also be taken into account.
The goal is to select a medication that offers an appropriate balance between expected therapeutic benefits and potential risks. In some conditions, medication is the primary treatment, while in others psychotherapy may be preferred or combined with pharmacological intervention.
Side Effects and Medical Monitoring
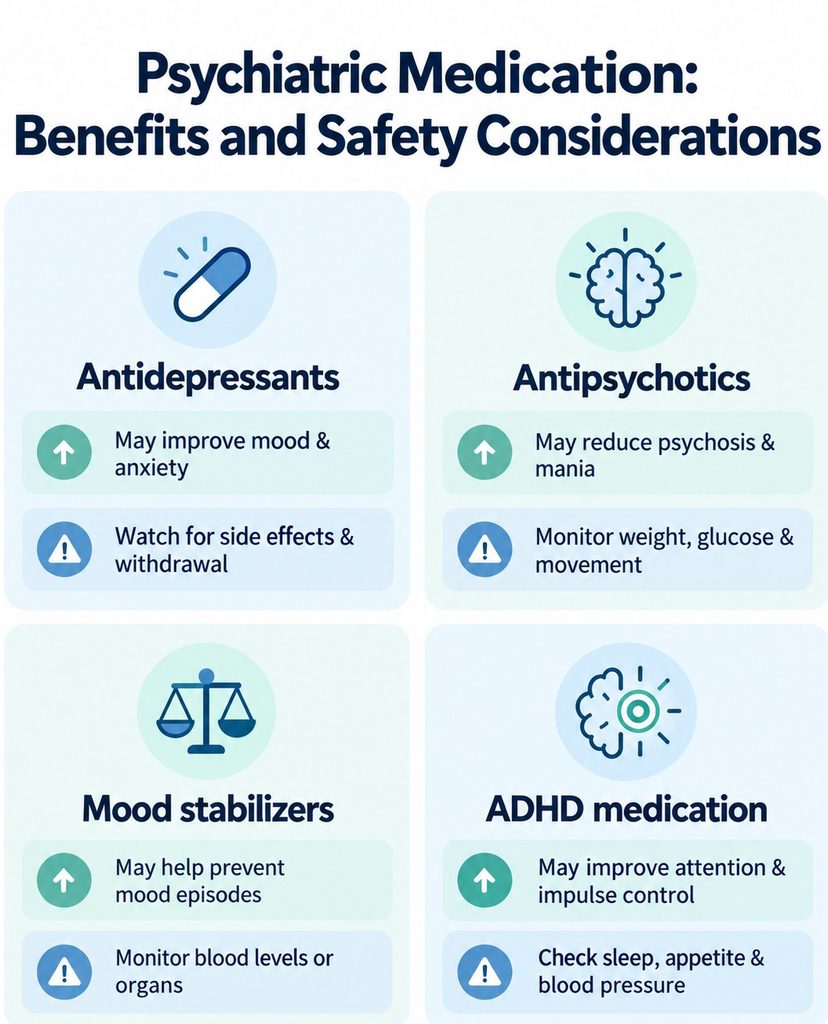
All psychiatric medications can cause adverse effects, although their frequency and severity vary substantially between drugs and individuals. Some side effects appear shortly after treatment begins and improve as the body adapts, while others emerge gradually or become more relevant during long-term use.
Regular follow-up consultations allow the psychiatrist to evaluate treatment response, identify adverse effects and determine whether dosage adjustments or medication changes are necessary. Depending on the medication and clinical circumstances, monitoring may include blood pressure, pulse, body weight, blood glucose, lipid levels, kidney or liver function, thyroid function, blood counts or an ECG.
Not every patient requires the same investigations. Monitoring should reflect the medication’s known risks, the patient’s medical history and any symptoms that develop during treatment. For example, lithium requires regular blood concentration and kidney function monitoring, while certain antipsychotics call for particular attention to metabolic changes.
The presence of side effects does not automatically mean that treatment must be discontinued, as adjustments may improve tolerability. However, severe allergic reactions, suspected medication toxicity, significant changes in consciousness or other serious symptoms require prompt medical evaluation.

Can Psychiatric Medication Cause Dependence?
The potential for dependence differs considerably between psychiatric medication groups. Benzodiazepines and certain sleeping medications can cause tolerance, physical dependence and withdrawal symptoms, particularly after repeated or prolonged use. Stimulant medications also have misuse and dependence potential, although appropriately supervised ADHD treatment differs substantially from non-medical stimulant use.
Antidepressants, antipsychotics and mood stabilizers are generally not considered addictive in the same way as medications that produce reinforcing intoxicating effects. Nevertheless, stopping these medications abruptly may cause withdrawal symptoms or increase the risk of recurrence of the underlying psychiatric disorder.
It is important to distinguish addiction, physical dependence and medication withdrawal, as these terms describe different phenomena. Addiction involves compulsive substance use despite harmful consequences, whereas physical dependence refers to physiological adaptation that may result in withdrawal symptoms when a medication is reduced or discontinued.
Patients should therefore avoid changing or stopping prescribed psychiatric medication independently, even when symptoms have improved or the medication is not considered addictive.
Psychiatric Medication During Pregnancy and Breastfeeding
The use of psychiatric medication during pregnancy and breastfeeding requires careful consideration of both the potential risks of treatment and the consequences of untreated mental illness. Severe depression, bipolar disorder and psychotic disorders may pose significant risks when treatment is interrupted, particularly in patients with a history of relapse.
At the same time, some psychiatric medications have established reproductive risks. Valproate, for example, is associated with major fetal developmental risks and is subject to strict prescribing precautions. Other medications may be continued during pregnancy when their expected benefits outweigh potential risks, taking account of the patient’s diagnosis, previous response and available safety evidence.
During breastfeeding, medication selection depends on factors such as transfer into breast milk, the infant’s age and health, and the mother’s treatment requirements. Patients planning pregnancy, currently pregnant or breastfeeding should therefore discuss their medication with their psychiatrist rather than discontinuing treatment without supervision.
When appropriate, psychiatric treatment should be coordinated with obstetric and other relevant medical care to support the wellbeing of both mother and child.
Psychiatric Medication in Older Adults
Psychiatric medication can remain effective in older adults, but prescribing often requires additional attention to age-related physiological changes, coexisting medical conditions and interactions between medications. Changes in kidney and liver function, body composition and sensitivity to certain drugs may influence their distribution, effectiveness and elimination.
Older patients are also more likely to take several medications simultaneously, increasing the risk of adverse interactions. Sedating drugs may contribute to falls, confusion and impaired coordination, while medications with anticholinergic effects can worsen constipation, urinary difficulties and cognitive impairment.
For these reasons, treatment often begins with a relatively low dose, followed by gradual adjustment according to clinical response and tolerability. However, doses must still be sufficient to achieve an appropriate therapeutic effect, as excessive caution can leave significant psychiatric symptoms untreated.
Regular medication reviews are particularly valuable in older adults to assess whether each medication remains necessary, effective and compatible with the patient’s overall health. Coordination between treating physicians can help reduce avoidable adverse effects and unnecessary polypharmacy.
How Long Should Psychiatric Medication Be Taken?
The appropriate duration of psychiatric medication depends on the diagnosis, severity and course of illness, previous episodes and individual treatment response. There is no universal treatment period that applies to every psychiatric disorder or medication.
In depression, antidepressant treatment is generally continued after remission to reduce the likelihood of relapse, while recurrent or chronic illness may require longer-term maintenance therapy. Bipolar disorder often requires prolonged treatment because the vulnerability to further mood episodes persists even after symptoms resolve. Similarly, patients with schizophrenia or recurrent psychotic disorders may benefit from sustained antipsychotic treatment.
By contrast, benzodiazepines and certain sleeping medications are generally intended for short-term use in most presentations of anxiety and insomnia because of their dependence and safety risks.
Decisions about continuing treatment should consider not only current symptom improvement but also the consequences of potential relapse, the patient’s treatment history and the tolerability of medication. Regular reviews help ensure that treatment duration remains appropriate rather than being determined by a fixed schedule.
How Should Psychiatric Medication Be Discontinued?
Discontinuation should be planned according to the medication, treatment duration, current dose and patient’s clinical condition. Gradual dose reduction is often recommended because abrupt changes can cause withdrawal symptoms or increase the risk of relapse.
The appropriate tapering schedule varies considerably between medications. Some can be reduced relatively quickly, whereas others require slower changes, particularly after prolonged treatment or previous withdrawal difficulties. Serious adverse effects may occasionally require a different approach.
Improvement in symptoms does not necessarily mean that medication is no longer needed. The decision to discontinue treatment should therefore be based on a careful assessment of sustained recovery, relapse risk and the availability of continuing psychiatric or psychological support.
Four steps for safely discontinuing psychiatric medication: individual assessment, gradual dose reduction, monitoring for withdrawal or relapse and ongoing support.

Psychiatric Medication and Psychotherapy
Psychiatric medication and psychotherapy address different but frequently complementary aspects of mental illness. Medication can reduce symptoms affecting mood, cognition, anxiety or behavioural control, while psychotherapy helps patients understand and modify psychological processes that may contribute to their difficulties.
The relative importance of medication and psychotherapy depends on the diagnosis, symptom severity and individual circumstances. Psychotherapy may be the preferred initial treatment for some conditions, whereas others require pharmacological intervention or benefit from a combination of approaches.
For depression, panic disorder and OCD, combined treatment may be appropriate depending on the clinical presentation and previous response. In bipolar disorder, psychotherapy can complement medication by improving illness understanding, helping patients recognise early warning signs and supporting long-term treatment adherence.
Medication does not automatically replace psychotherapy, and psychotherapy does not always remove the need for medication. An individualised treatment plan considers the contribution of both approaches rather than treating them as competing alternatives.
Psychiatric Medication at CHMC German Clinic in Dubai
At CHMC German Clinic for Psychiatry and Psychology in Dubai, psychiatric medication is prescribed and monitored by Dr. Gregor Kowal, German Board-Certified Consultant Psychiatrist and Psychotherapist. With more than 30 years of clinical experience in Germany and the UAE, Dr. Kowal integrates psychiatric expertise with a comprehensive understanding of psychological treatment.
Treatment begins with a detailed psychiatric assessment intended to establish an accurate diagnosis and identify factors that may influence medication selection. Particular attention is given to disorders with overlapping symptoms, previous treatment responses, coexisting medical conditions and potential contraindications. This diagnostic approach helps avoid prescribing medication solely on the basis of isolated symptoms.
When pharmacological treatment is indicated, medication is selected according to the patient’s clinical condition, expected benefits, potential adverse effects and individual circumstances. Dosages are adjusted progressively when appropriate, taking account of both therapeutic response and tolerability. The treatment plan also considers whether medication should be combined with psychotherapy.
Regular follow-up consultations provide an opportunity to evaluate improvement, identify side effects and reassess the continued need for treatment. Laboratory investigations, ECGs and other medical assessments are arranged when clinically indicated, while medication changes or discontinuation are planned according to the patient’s condition and relapse risk.
The objective of psychiatric medication treatment at CHMC Dubai is to achieve sustained improvement while minimising avoidable risks and unnecessary medication exposure. Patients seeking an initial psychiatric assessment, medication review or second opinion can contact the clinic to arrange a consultation with Dr. Kowal.
Frequently Asked Questions About Psychiatric Medication
Are psychiatric medications safe?
Psychiatric medications can be safe and effective when prescribed for appropriate clinical indications and monitored according to their known risks. However, all medications may cause adverse effects, and their suitability depends on the patient’s diagnosis, medical history, other medications and individual circumstances.
How long does psychiatric medication take to work?
The onset of action varies between medication groups. Benzodiazepines and stimulant medications may produce noticeable effects within hours, while antidepressants usually require several weeks for substantial improvement. Medications used for relapse prevention may also provide benefits that become apparent over longer periods.
Do psychiatric medications change your personality?
Psychiatric medications are intended to reduce symptoms rather than alter personality. Successful treatment may help patients regain emotional stability, motivation and everyday functioning. However, some medications can produce unwanted experiences such as emotional blunting, sedation or reduced spontaneity, which should be discussed with the treating psychiatrist.
Can psychiatric medication be taken for life?
Some psychiatric conditions require long-term or lifelong medication, particularly when the risk of relapse remains high. Other patients may need treatment only for a limited period. The decision depends on the diagnosis, course of illness, medication response and potential consequences of discontinuation.
Can psychiatric medication be combined with psychotherapy?
Yes. Psychiatric medication and psychotherapy are frequently combined when clinically appropriate because they can address different aspects of a mental disorder. The need for combined treatment depends on symptom severity, diagnosis, treatment goals and individual preferences.
Can I stop psychiatric medication when I feel better?
Symptom improvement does not necessarily mean that medication can be stopped immediately. Some disorders remain vulnerable to recurrence after recovery, while abrupt discontinuation may cause withdrawal symptoms. Medication reduction or discontinuation should therefore be planned with the prescribing psychiatrist.
Conclusion: Safe and Effective Use of Psychiatric Medication
Psychiatric medications are an important part of modern mental healthcare and can substantially improve symptoms and everyday functioning in patients with a wide range of psychiatric disorders. Their effectiveness, however, depends on selecting the appropriate treatment for the underlying diagnosis and adapting it to the patient’s individual needs.
Accurate psychiatric assessment, careful medication selection, appropriate medical monitoring and regular treatment reviews are essential for achieving therapeutic benefits while reducing unnecessary risks. Psychotherapy may provide additional benefits, particularly when psychological factors contribute to persistent symptoms or difficulties in everyday life.
At CHMC German Clinic for Psychiatry and Psychology in Dubai, psychiatric medication is integrated into an individualised treatment approach that considers the biological, psychological and medical aspects of mental health. Patients considering medication, experiencing side effects or seeking a review of their current treatment can arrange a specialist psychiatric consultation.


