

Depression and bipolar disorder are two distinct psychiatric illnesses that can produce remarkably similar symptoms. Patients with either condition may experience persistent sadness, loss of interest, fatigue, disturbed sleep, poor concentration, and feelings of hopelessness. During a depressive episode, the two conditions can appear almost identical, making it difficult to distinguish between them based on current symptoms alone.
The main difference between depression and bipolar disorder is the presence of manic or hypomanic episodes. People with major depressive disorder, also called unipolar depression, experience depressive episodes without a history of mania or hypomania. People with bipolar disorder, by contrast, have experienced at least one manic or hypomanic episode, although depression may remain their predominant complaint.
This distinction is particularly important because many patients with bipolar disorder first seek psychiatric help during a depressive episode. Previous periods of unusually elevated mood or increased energy may have been perceived as normal or even beneficial and therefore remain unrecognised. As a result, bipolar disorder, particularly bipolar II disorder, is sometimes mistaken for recurrent major depressive disorder.
An accurate diagnosis is essential because the treatment approaches differ considerably. While major depressive disorder is commonly treated with psychotherapy and antidepressants, bipolar disorder generally requires mood-stabilising medication, careful psychiatric monitoring, and long-term relapse prevention.
In this article, Dr. Gregor Kowal, German Board-Certified Consultant Psychiatrist and Psychotherapist at CHMC Dubai, explains the differences between depression and bipolar depression, the clinical signs that may suggest bipolar disorder, and how psychiatrists establish the correct diagnosis.
For psychiatric assessment contact our consultant psychiatrist Dr. Kowal
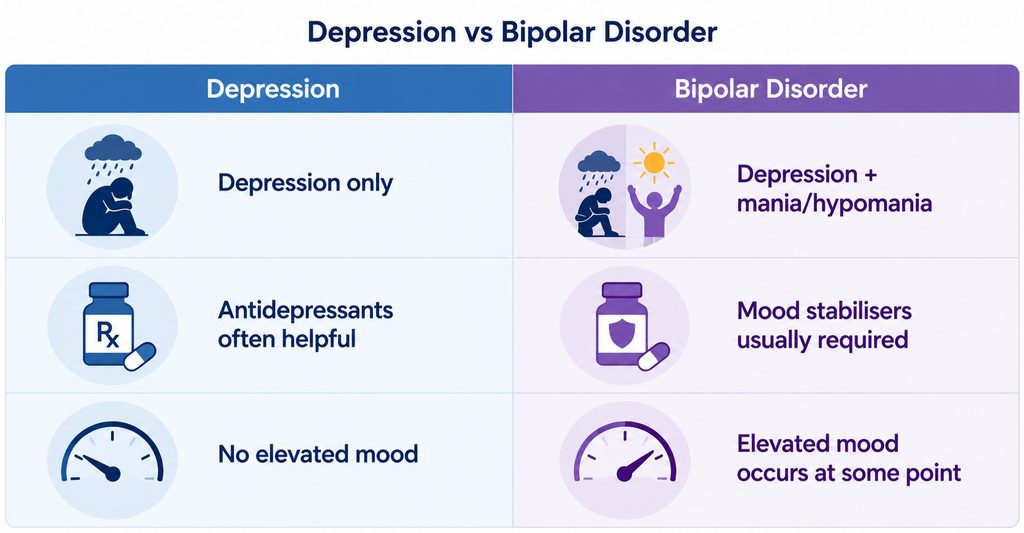
What Is the Difference Between Depression and Bipolar Disorder?
The central distinction between depression and bipolar disorder concerns the patient’s history of mood episodes rather than the severity of the depressive symptoms themselves. Both illnesses can cause profound emotional suffering and interfere with work, relationships, and everyday activities. However, bipolar disorder also involves episodes of abnormally elevated or irritable mood accompanied by increased energy or activity.
In major depressive disorder, patients experience depressive episodes without previous mania or hypomania. Some patients recover completely after one episode, whereas others develop recurrent depression over many years. Although their mood may fluctuate, these changes do not meet the diagnostic criteria for mania or hypomania.
In bipolar disorder, depressive episodes occur within an illness that also includes manic or hypomanic episodes. During these periods, patients may feel unusually energetic, confident, creative, or productive. They may need considerably less sleep, talk more rapidly, become more socially active, or engage in impulsive behaviour. These changes are sometimes recognised by family members before the patient becomes aware of them.
The distinction cannot always be established during the first consultation. A psychiatrist must therefore investigate not only the patient’s current depression but also previous mood episodes, changes in sleep and behaviour, family history, and responses to earlier treatment.
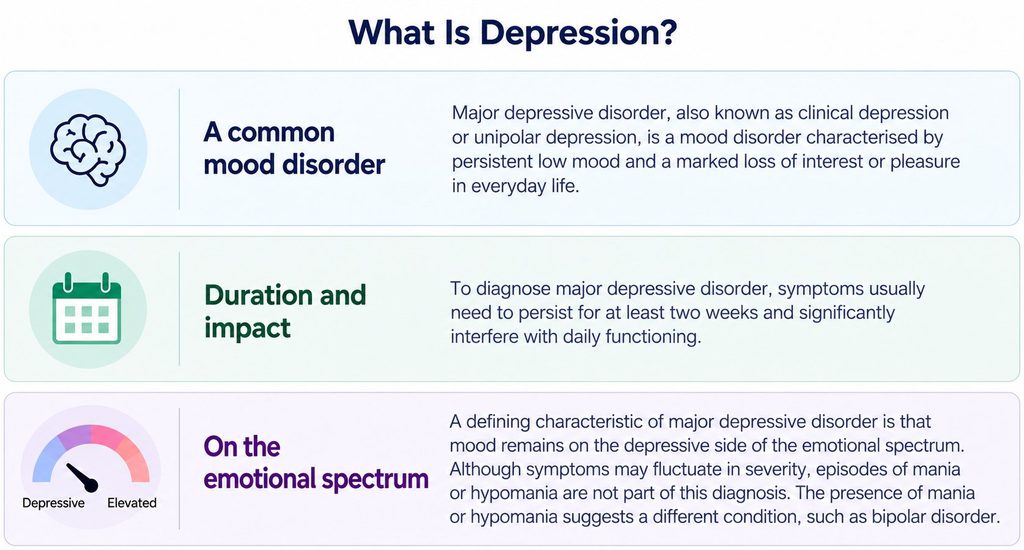
What Is Unipolar Depression?
“Common” depression, also known as major depressive disorder or unipolar depression, is a psychiatric illness characterised by persistent low mood or a marked loss of interest and pleasure in everyday activities. Unlike ordinary sadness following disappointment or stressful life events, clinical depression affects emotional well-being, physical health, thinking, behaviour, and the ability to function in everyday life.
Patients often describe feeling exhausted, emotionally numb, or unable to enjoy activities that previously gave them satisfaction. Concentration and decision-making may become difficult, while even simple responsibilities can feel overwhelming. Sleep and appetite frequently change, and some patients experience pronounced feelings of guilt, worthlessness, or hopelessness. In severe cases, depression may be accompanied by suicidal thoughts.
For a depressive episode to be diagnosed, characteristic symptoms must generally persist for at least two weeks and cause significant distress or impairment. However, the duration and severity of depression vary considerably between patients. Some recover after a single episode, while others experience recurrent episodes separated by months or years of relative well-being.
A defining feature of major depressive disorder is the absence of a history of mania or hypomania. If a patient later develops a confirmed manic or hypomanic episode, the previous diagnosis must be reconsidered because the depression may have been part of an underlying bipolar disorder.
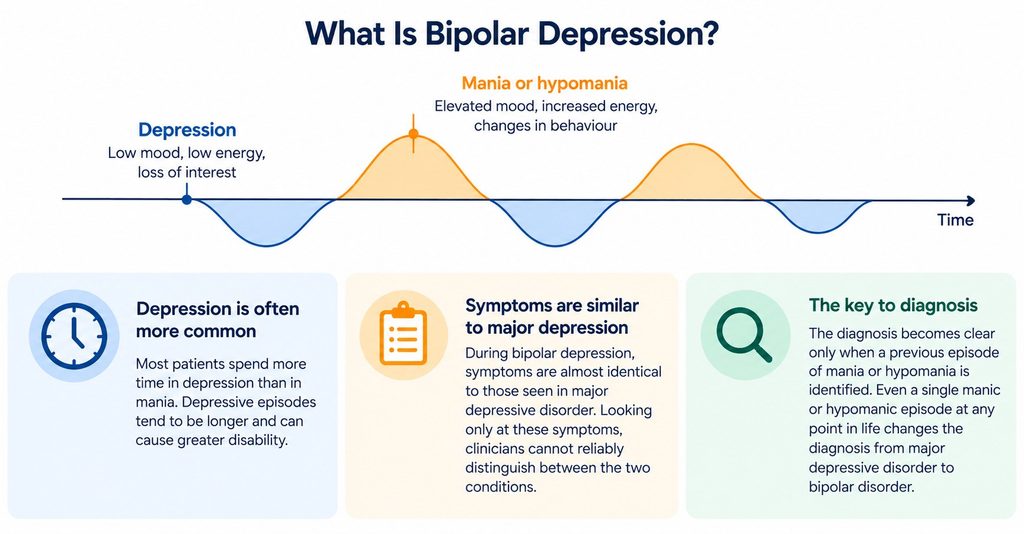
What Is Bipolar Depression?
Bipolar depression refers to a depressive episode occurring in a person with bipolar disorder. During these episodes, patients experience symptoms very similar to those of major depressive disorder, including persistent sadness, loss of interest, fatigue, poor concentration, disturbed sleep, and reduced motivation. Some patients withdraw almost completely from social activities and struggle to maintain their professional and personal responsibilities.
Although bipolar disorder is commonly associated with mania and excessive energy, depressive episodes frequently account for a substantial part of the illness burden. For many patients, depression is more prolonged and disabling than periods of elevated mood. This is particularly apparent in bipolar II disorder, where patients may experience severe recurrent depression while their hypomanic episodes remain relatively mild and easily overlooked.
The diagnosis of bipolar disorder does not depend on the depressive symptoms alone. It requires identifying a history of mania or hypomania and evaluating the overall course of the illness. Understanding the difference between bipolar I and bipolar II disorder is therefore essential.
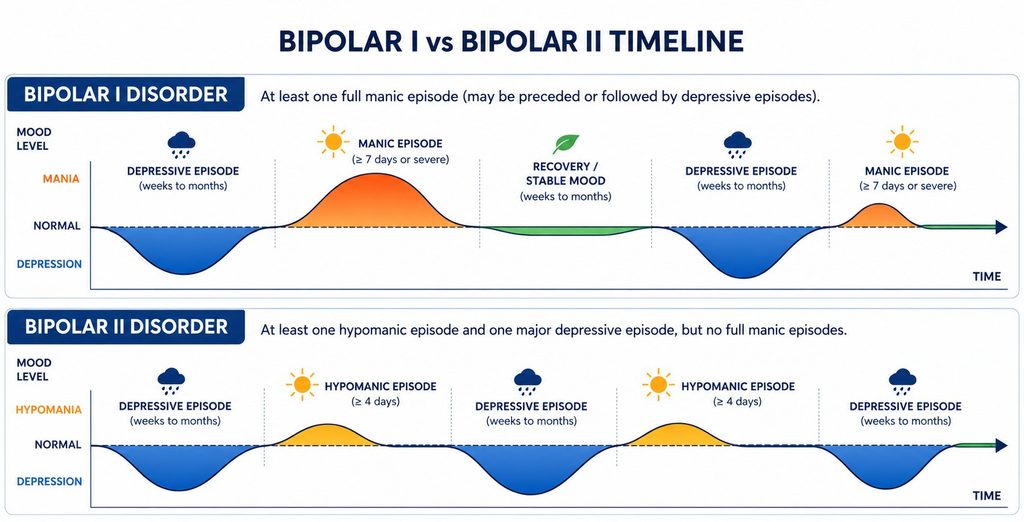
Bipolar I Disorder
Bipolar I disorder is defined by the occurrence of at least one manic episode. During mania, mood becomes abnormally elevated, expansive, or irritable, and energy and activity increase considerably. Patients may feel unusually powerful, confident, or capable of achieving almost anything, while their need for sleep decreases dramatically.
Thoughts and speech often become unusually rapid, and patients may start numerous projects without completing them. Judgment can become impaired, leading to excessive spending, unrealistic business plans, risky behaviour, or serious interpersonal conflicts. In severe cases, mania may be accompanied by psychotic symptoms, including delusions, and hospital treatment may become necessary.
Many patients with bipolar I disorder also experience major depressive episodes, which may be prolonged and severely disabling. However, a depressive episode is not required for the diagnosis. The defining clinical feature is the history of mania.
Bipolar II Disorder
Bipolar II disorder is characterised by at least one major depressive episode and at least one hypomanic episode, without a history of full mania. Hypomania is a less severe form of mood elevation that lasts at least four consecutive days and involves a noticeable change in mood, energy, and behaviour.
During hypomania, patients may feel unusually productive, creative, confident, sociable, or energetic. They often sleep considerably less than usual without feeling tired and may complete more work, become more talkative, or engage in new activities. Unlike full mania, hypomania does not cause marked impairment in functioning or require hospitalisation.
Because these periods can feel pleasant and beneficial, patients rarely seek medical help during hypomania. They may consider the increased energy and confidence part of their normal personality rather than recognising them as symptoms of a mood disorder.
The depressive episodes associated with bipolar II disorder, however, can be severe and prolonged. Consequently, many patients seek psychiatric treatment for recurrent depression without mentioning their previous hypomanic episodes. This is one of the main reasons why bipolar II disorder is frequently mistaken for major depressive disorder.
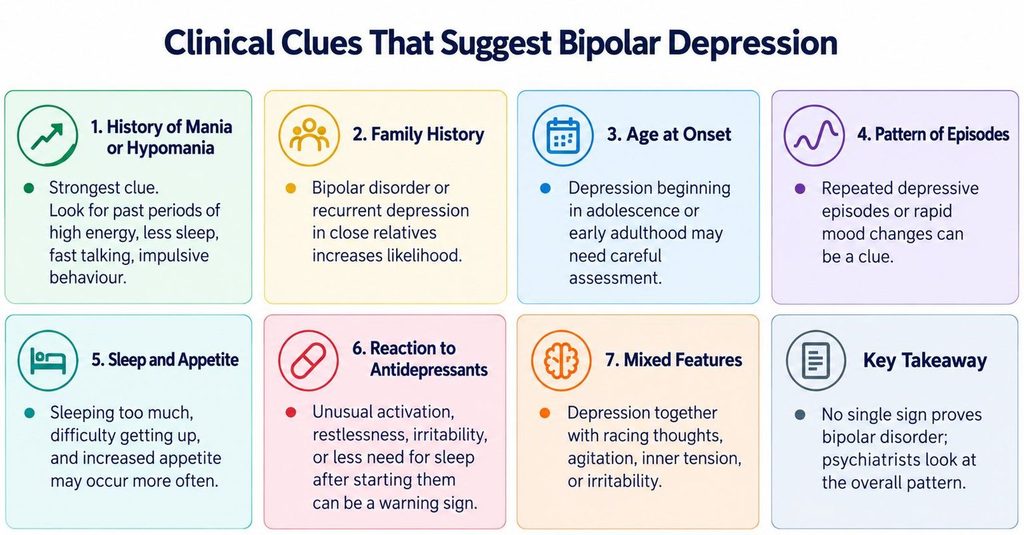
Clinical Clues That Suggest Bipolar Depression
Since depressive symptoms alone cannot reliably distinguish bipolar depression from major depressive disorder, psychiatrists pay particular attention to the patient’s history and the pattern of previous mood episodes. Several clinical characteristics may raise suspicion of bipolar disorder, although none of them independently establishes the diagnosis.
Previous Episodes of Mania or Hypomania
The most important indicator of bipolar disorder is a history of mania or hypomania. Many patients initially do not remember these episodes as abnormal because they experienced them as periods of increased productivity, confidence, or well-being.
When asked specific questions, patients may recall phases in which they slept only a few hours each night without feeling tired, talked excessively, became unusually sociable, started numerous projects, or made impulsive decisions. Others remember periods of irritability, excessive spending, or unusually ambitious plans that differed markedly from their usual behaviour.
Recognising these episodes requires a careful psychiatric interview because patients may never have considered them symptoms of illness. The psychiatrist must establish whether the reported changes represent genuine manic or hypomanic episodes rather than ordinary fluctuations in mood or activity.
Family History of Bipolar Disorder
Bipolar disorder has a strong hereditary component, making family history an important part of psychiatric assessment. Patients who have close biological relatives with bipolar disorder are at increased risk of developing the illness themselves.
A family history of recurrent depression, severe mood disturbances, psychiatric hospitalisation, or suicide may also provide useful information, although these findings are less specific. The psychiatrist considers this background together with the patient’s current symptoms and previous mood episodes.
Family history alone cannot confirm bipolar disorder. Nevertheless, it may strengthen clinical suspicion, particularly when a patient presents with recurrent depression and other features suggestive of bipolar illness.
Age at Which Depression First Appeared
Bipolar disorder often begins during adolescence or early adulthood, although it can develop later in life. Patients who experience their first depressive episode at a young age, particularly before the age of 25, may warrant closer evaluation for possible bipolar disorder.
This is especially relevant when early-onset depression is accompanied by recurrent episodes, a family history of bipolar disorder, or periods of unusually increased energy and reduced need for sleep.
However, major depressive disorder also frequently begins during adolescence or young adulthood. The age of onset is therefore only one element of the diagnostic assessment and should never be used in isolation.
Pattern of Depressive Episodes
The frequency and course of depressive episodes can provide additional diagnostic information. Bipolar disorder is often associated with recurrent mood episodes, and some patients experience repeated periods of depression separated by intervals of relatively normal functioning.
Others may develop several mood episodes within one year, sometimes alternating between depression and elevated mood. When four or more distinct mood episodes occur within twelve months, the pattern may meet the criteria for rapid cycling.
However, recurrent depressive episodes are also common in major depressive disorder. The psychiatrist therefore examines the entire course of the illness rather than assuming that frequent depression necessarily indicates bipolar disorder.
Sleep Patterns and Changes in Appetite
Disturbances in sleep and appetite occur in both major depressive disorder and bipolar depression. Some patients experience insomnia and reduced appetite, while others sleep excessively, gain weight, and struggle with persistent fatigue.
Excessive sleeping and increased appetite may be somewhat more common in bipolar depression, but these characteristics are not sufficiently specific to establish the diagnosis.
More important is a history of periods during which the patient required much less sleep than usual while remaining energetic and active. This reduced need for sleep is a characteristic feature of mania and hypomania and differs from insomnia, where the person usually feels tired but cannot sleep.
Unusual Reactions to Antidepressants
The patient’s response to previous antidepressant treatment may provide important diagnostic clues. Occasionally, patients who are being treated for depression develop unusual increases in energy, agitation, irritability, rapid speech, or a markedly reduced need for sleep after starting an antidepressant.
Such reactions may reflect medication-related activation, side effects, or emerging manic or hypomanic symptoms. They do not automatically establish a diagnosis of bipolar disorder, but they require careful psychiatric evaluation.
The psychiatrist examines the nature, duration, and severity of these changes and considers whether they indicate an underlying vulnerability to bipolar disorder. This information is particularly important when selecting further treatment.
Depression With Mixed Features
Some patients experience depressive symptoms together with symptoms usually associated with mania or hypomania. They may feel deeply unhappy or hopeless while simultaneously experiencing racing thoughts, marked agitation, increased energy, or a reduced need for sleep.
This combination is known as depression with mixed features. It can occur in both major depressive disorder and bipolar disorder, but its presence requires careful evaluation because it may influence medication selection and clinical risk.
Patients with mixed features may experience considerable inner tension and impulsivity, particularly when severe depression is also present. Careful assessment and monitoring are therefore important, especially when suicidal thoughts or behavioural instability develop.

Why Is Bipolar Disorder Often Misdiagnosed as Depression?
One of the greatest challenges in diagnosing bipolar disorder is that patients usually seek psychiatric help during depressive episodes rather than during mania or hypomania. Depression causes emotional suffering, hopelessness, loss of motivation, and significant impairment in everyday functioning, naturally encouraging patients to seek medical treatment.
Hypomania, by contrast, may be experienced as a period of exceptionally good functioning. Individuals can feel more confident, energetic, productive, sociable, or creative than usual. Since these changes may initially appear beneficial, patients often do not consider them symptoms of illness and rarely mention them spontaneously during psychiatric consultations.
This creates a situation in which the psychiatrist initially hears a detailed history of recurrent depression but receives little information about previous elevated mood episodes. Without specifically investigating mania and hypomania, bipolar disorder may remain unrecognised, sometimes for many years.
The problem is particularly relevant in bipolar II disorder, where hypomanic episodes are less disruptive than full mania and may never lead to hospitalisation or obvious social consequences.
Another difficulty is that patients may have reduced awareness of their behavioural changes during elevated mood. Family members sometimes recognise these changes more readily and describe excessive confidence, impulsive spending, unusual activity, irritability, or markedly reduced sleep.
For this reason, psychiatrists frequently encourage patients to involve a partner or close family member in the diagnostic assessment, provided the patient agrees. Information from relatives may reveal previous manic or hypomanic episodes that would otherwise remain unnoticed.
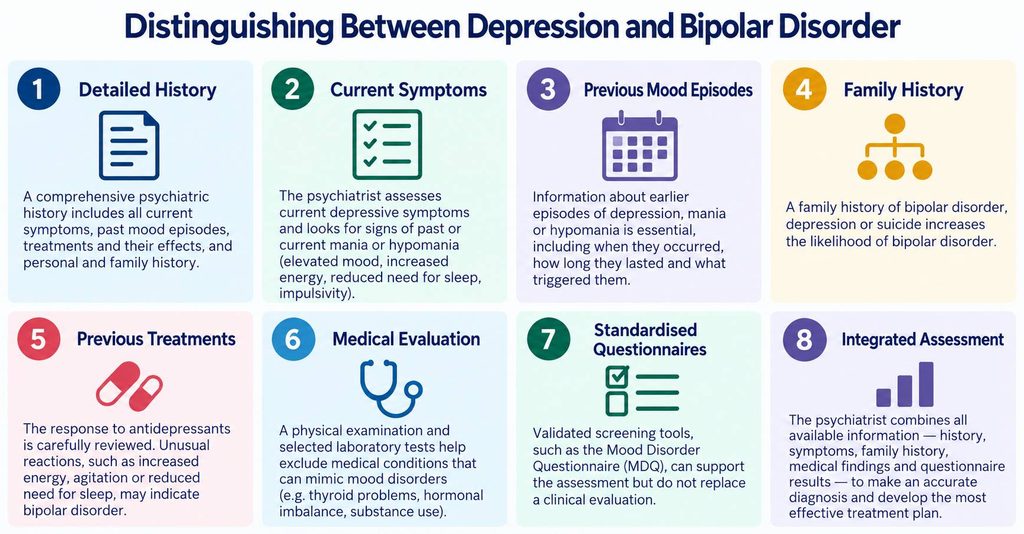
How Do Psychiatrists Distinguish Depression From Bipolar Disorder?
There is currently no laboratory investigation, blood test, or brain scan that can reliably distinguish major depressive disorder from bipolar disorder. The diagnosis is primarily clinical and depends on a comprehensive assessment of the patient’s psychiatric history, present symptoms, and the course of the illness over time.
A detailed psychiatric evaluation is particularly important when someone presents with recurrent depression, an unusual response to antidepressants, a family history of bipolar disorder, or previous periods of markedly increased energy.
Detailed Psychiatric Interview
The psychiatrist begins by exploring the current depressive symptoms, including their onset, severity, duration, and impact on daily functioning. Particular attention is given to sleep, appetite, concentration, motivation, and any symptoms suggesting increased clinical risk.
The assessment then extends beyond the current depressive episode to examine the patient’s entire mood history. Questions focus on previous periods of unusually elevated or irritable mood, increased energy, excessive activity, reduced need for sleep, impulsive decisions, and changes in behaviour.
Many patients initially deny having experienced hypomania because they associate the term with extreme manic behaviour. However, when asked about specific experiences, such as sleeping very little while remaining energetic or becoming unusually productive and confident, they may recognise periods that deserve further investigation.
The psychiatrist must determine whether these changes represented clearly defined mood episodes with sufficient duration and associated symptoms, rather than ordinary variations in personality or everyday mood.
Reviewing Previous Mood Episodes
The psychiatrist also investigates when depressive symptoms first appeared, how frequently episodes have returned, and whether there were periods of complete or partial recovery between them.
Understanding the sequence of previous mood episodes can provide valuable information. Some patients experience depression for several years before their first recognisable manic or hypomanic episode, while others recall periods of increased energy long before seeking treatment.
The duration and severity of elevated mood episodes are particularly important when distinguishing bipolar I from bipolar II disorder. A history of full mania supports bipolar I disorder, whereas bipolar II requires a history of hypomania and major depression without full mania.
Family History and Information From Relatives
Family history is an important part of the assessment because bipolar disorder frequently occurs among biological relatives. The psychiatrist asks about previous diagnoses of bipolar disorder, recurrent depression, psychiatric hospitalisation, and other significant mood disturbances within the family.
Whenever appropriate and with the patient’s consent, information may also be obtained from a partner or close family member. Relatives sometimes remember periods of unusual activity, excessive confidence, impulsive behaviour, or reduced sleep that the patient did not recognise as abnormal.
These observations are especially helpful when insight was reduced during previous manic or hypomanic episodes.
Reviewing Previous Treatments
The psychiatrist evaluates earlier treatments, including antidepressants, mood stabilisers, antipsychotic medications, and psychotherapy. Attention is given to the effectiveness of treatment, adverse effects, and any unexpected changes in mood or behaviour.
A history of unusually increased energy, agitation, irritability, or reduced need for sleep following antidepressant treatment may raise suspicion of bipolar disorder. However, these reactions must be interpreted carefully because they can also occur for other reasons.
Previous treatment responses provide supporting information but cannot independently determine the diagnosis.
Screening Questionnaires
Standardised questionnaires, including the Mood Disorder Questionnaire (MDQ) and the Bipolar Spectrum Diagnostic Scale (BSDS), may be used to support the psychiatric assessment.
These instruments help identify symptoms that require further investigation, particularly when patients have difficulty remembering or recognising previous hypomanic episodes.
However, screening questionnaires cannot establish or exclude bipolar disorder on their own. Their results must always be interpreted within the context of a comprehensive clinical interview.
Excluding Other Medical and Psychiatric Conditions
Several medical and psychiatric conditions can cause symptoms resembling depression, mania, or hypomania. Thyroid disorders, certain medications, substance use, sleep disorders, and other psychiatric illnesses may influence mood, energy, and behaviour.
Depending on the clinical findings, the psychiatrist may recommend a physical examination, blood tests, thyroid function tests, or additional medical investigations.
These examinations do not directly diagnose bipolar disorder but help exclude alternative explanations and identify medical factors that may influence treatment.
Why Diagnosis Sometimes Takes Time
In some patients, the distinction between major depressive disorder and bipolar disorder cannot be established confidently during the first consultation. This is particularly true when someone presents with depression but has never experienced a clearly recognisable manic or hypomanic episode.
Psychiatric diagnoses sometimes become clearer only after reviewing previous medical records, obtaining additional information from relatives, or observing changes in mood over time.
For this reason, careful follow-up is essential when the clinical history raises suspicion of bipolar disorder but the available information is not yet sufficient to confirm the diagnosis.
Depression vs Bipolar Disorder: Treatment Differences
Correctly distinguishing major depressive disorder from bipolar disorder has important consequences for treatment. Although both illnesses can cause severe depressive symptoms, their long-term management differs because bipolar disorder also involves a vulnerability to manic or hypomanic episodes.
A treatment that is effective for major depressive disorder may be less suitable for bipolar depression, particularly when there is a risk of triggering elevated mood or increasing mood instability.
Treatment of Major Depressive Disorder
Major depressive disorder is commonly treated with psychotherapy, antidepressant medication, or a combination of both. The selection of treatment depends on the severity of depression, previous episodes, the patient’s medical history, and individual preferences.
Antidepressants, particularly selective serotonin reuptake inhibitors (SSRIs), are frequently prescribed when medication is indicated. They aim to reduce depressive symptoms and support recovery of emotional and everyday functioning.
Psychotherapy is also an important treatment option, helping patients understand emotional difficulties, address unhelpful thinking patterns, improve coping strategies, and gradually return to normal activities.
Patients with severe or recurrent depression may require longer-term treatment and regular follow-up to reduce the likelihood of relapse.

Medication for Bipolar Depression
Treatment of bipolar depression requires a different approach because medication must address depressive symptoms while also considering the risk of mania, hypomania, and future mood episodes.
Depending on the clinical presentation, treatment may include mood stabilisers such as lithium or lamotrigine and selected second-generation antipsychotic medications with demonstrated effectiveness in bipolar depression.
These medications are selected according to the type of bipolar disorder, the severity of the current episode, previous treatment responses, and possible adverse effects. Not every medication that prevents mania is equally effective against bipolar depression, making individual treatment planning essential.
Antidepressants require particular caution in bipolar disorder. In susceptible patients, they may contribute to manic or hypomanic symptoms or increased mood instability. Antidepressant monotherapy is therefore generally avoided in bipolar I depression, while antidepressants may be considered in selected patients under appropriate psychiatric supervision.
The aim of treatment is not only to relieve the current depression but also to reduce the risk of future depressive and elevated mood episodes.
Psychotherapy in Depression and Bipolar Disorder
Psychotherapy plays an important role in both conditions, although the therapeutic focus may differ.
In major depressive disorder, psychotherapy often addresses depressive thought patterns, emotional conflicts, stressful life experiences, interpersonal difficulties, and strategies for preventing future depressive episodes.
In bipolar disorder, psychotherapy additionally helps patients recognise early warning signs of mania or depression, maintain regular sleep and daily routines, manage stress, and improve adherence to long-term treatment.
Psychological support can also help patients and their families understand the illness, respond more effectively to mood changes, and reduce the effects of bipolar disorder on relationships and everyday life.
Long-Term Psychiatric Monitoring
Long-term psychiatric monitoring is particularly important in bipolar disorder because the vulnerability to further mood episodes usually persists even during prolonged periods of recovery.
Regular follow-up allows the psychiatrist to assess mood stability, monitor medication effectiveness and side effects, and identify early warning signs of relapse before symptoms become severe.
Major depressive disorder may also require prolonged treatment, especially when depressive episodes recur or have been particularly severe.
For both illnesses, an individualised treatment plan, consistent follow-up, and timely adjustments to treatment can improve long-term outcomes and quality of life.

When Should You See a Psychiatrist?
Many people assume that all depressive episodes belong to the same illness. Consequently, they may not recognise that recurrent depression accompanied by previous periods of unusually high energy, reduced need for sleep, or impulsive behaviour could indicate bipolar disorder.
A psychiatric assessment is especially important when depressive episodes begin early in life, return repeatedly, or respond poorly to treatment. A family history of bipolar disorder or unusual reactions to antidepressant medication may also justify a more detailed evaluation.
Patients who have experienced periods of exceptionally increased energy, confidence, activity, or irritability should discuss these changes with a psychiatrist, even when the episodes appeared positive or did not cause obvious difficulties.
A comprehensive assessment can help distinguish major depressive disorder from bipolar disorder and identify the most appropriate treatment.
Anyone experiencing suicidal thoughts, psychotic symptoms, severe behavioural changes, or an inability to maintain personal safety should seek urgent psychiatric care. Immediate danger requires emergency medical assistance.
Psychiatric Assessment at CHMC Dubai
At CHMC German Clinic for Psychiatry and Psychology in Dubai, Dr. Gregor Kowal provides detailed psychiatric assessments for patients experiencing depression, recurrent mood episodes, or symptoms suggestive of bipolar disorder.
As a German Board-Certified Consultant Psychiatrist and Psychotherapist, Dr. Kowal evaluates current symptoms together with the patient’s previous mood episodes, sleep patterns, family history, response to earlier treatments, and overall psychiatric history.
When indicated, the assessment may also include information from family members and additional medical investigations. This comprehensive approach aims to establish the most accurate diagnosis possible and develop an individualised treatment plan based on the patient’s clinical needs.
Patients who are uncertain whether their symptoms represent major depressive disorder or bipolar depression may benefit from a specialist assessment before treatment decisions are made.
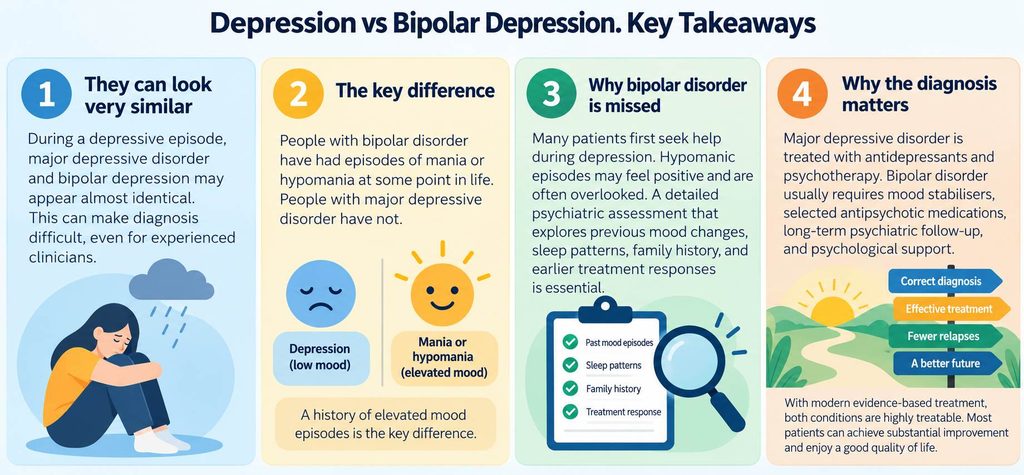
Depression vs Bipolar Depression: Key Takeaways
Although major depressive disorder and bipolar depression share many symptoms, they are different psychiatric illnesses that require different treatment approaches. During a depressive episode, they may appear almost identical, making a careful psychiatric history essential for establishing the diagnosis.
The defining difference is that bipolar disorder involves a history of mania or hypomania, whereas major depressive disorder does not. Because hypomanic episodes may feel pleasant or productive, patients often overlook them and seek treatment only when they become depressed. Information from family members and a review of previous mood episodes can therefore be particularly valuable.
Correct diagnosis has a direct impact on treatment. Major depressive disorder is commonly treated with psychotherapy and antidepressants, while bipolar disorder generally requires mood-stabilising medication, long-term psychiatric monitoring, and psychological support. Recognising bipolar disorder early helps avoid unsuitable treatment and supports more effective relapse prevention.
With modern evidence-based psychiatric care, many patients with either condition can achieve substantial improvement, return to productive work, maintain satisfying relationships, and enjoy a good quality of life.
FAQs About Depression vs Bipolar Disorder
What Is the Main Difference Between Depression and Bipolar Depression?
The main difference is the history of manic or hypomanic episodes. People with major depressive disorder experience depressive episodes without a history of mania or hypomania, whereas those with bipolar disorder have experienced at least one episode of elevated or irritable mood accompanied by increased energy. During depression, however, symptoms may appear almost identical.
Can Bipolar Depression Feel Exactly Like Major Depression?
Yes. Bipolar depression can produce the same sadness, fatigue, loss of interest, poor concentration, and sleep disturbances seen in major depressive disorder. The diagnosis cannot reliably be made from the depressive symptoms alone. A psychiatrist must also investigate previous episodes of elevated mood, increased energy, and reduced need for sleep.
Why Is Bipolar Disorder Often Misdiagnosed as Depression?
Many patients with bipolar disorder seek psychiatric help during depressive episodes because these cause considerable emotional suffering. Previous hypomanic episodes may have felt pleasant or productive and are often not mentioned during the consultation. Without a detailed history of mood changes, bipolar disorder may therefore be mistaken for recurrent major depressive disorder.
How Can a Psychiatrist Distinguish Bipolar Depression From Major Depression?
The psychiatrist examines the patient’s current symptoms, previous mood episodes, sleep patterns, family history, and responses to earlier treatments. Particular attention is given to periods of unusually increased energy, reduced need for sleep, and changes in behaviour. Information from relatives and screening questionnaires may support the assessment, but the diagnosis remains clinical.
Can Antidepressants Make Bipolar Disorder Worse?
In some patients, antidepressants can contribute to mania, hypomania, or increased mood instability. The risk depends on the type of bipolar disorder, the patient’s previous history, and the medication used. For this reason, antidepressants require careful consideration in bipolar depression and are generally not prescribed alone in bipolar I disorder.
Can Depression Later Be Diagnosed as Bipolar Disorder?
Yes. Some patients initially experience only depressive episodes and are diagnosed with major depressive disorder. If a manic or hypomanic episode later becomes apparent, the diagnosis may be revised to bipolar disorder. This does not mean that depression necessarily develops into bipolar disorder, but rather that the underlying illness may not have been recognisable during the earlier stages.
Can Psychotherapy Help Both Depression and Bipolar Disorder?
Psychotherapy is an important part of treatment for both conditions. In major depressive disorder, it helps patients address depressive thinking patterns, emotional difficulties, and coping strategies. In bipolar disorder, psychotherapy additionally supports recognition of early warning signs, regular sleep routines, stress management, medication adherence, and long-term relapse prevention.
xxxxxxxxxxxxxxxxxxxxxxxxxxxxxxxxxx
What Is Depression?
Depression, also known as major depressive disorder or unipolar depression, is a mood disorder characterised by persistent low mood and a marked loss of interest or pleasure in everyday life. Unlike normal sadness after disappointment or loss, depression is a medical illness that affects emotions, physical health, thinking, behaviour, relationships, and work performance.
To diagnose depression, symptoms usually need to persist for at least two weeks and significantly interfere with daily functioning. Many patients describe depression as feeling emotionally numb rather than simply sad. Activities they previously enjoyed no longer bring satisfaction, and even simple daily tasks can feel overwhelming.
A defining characteristic of major depressive disorder is that mood remains on the depressive side of the emotional spectrum. Although symptoms may fluctuate in severity, patients do not experience episodes of mania or hypomania. This is the most important distinction between major depressive disorder and bipolar disorder.
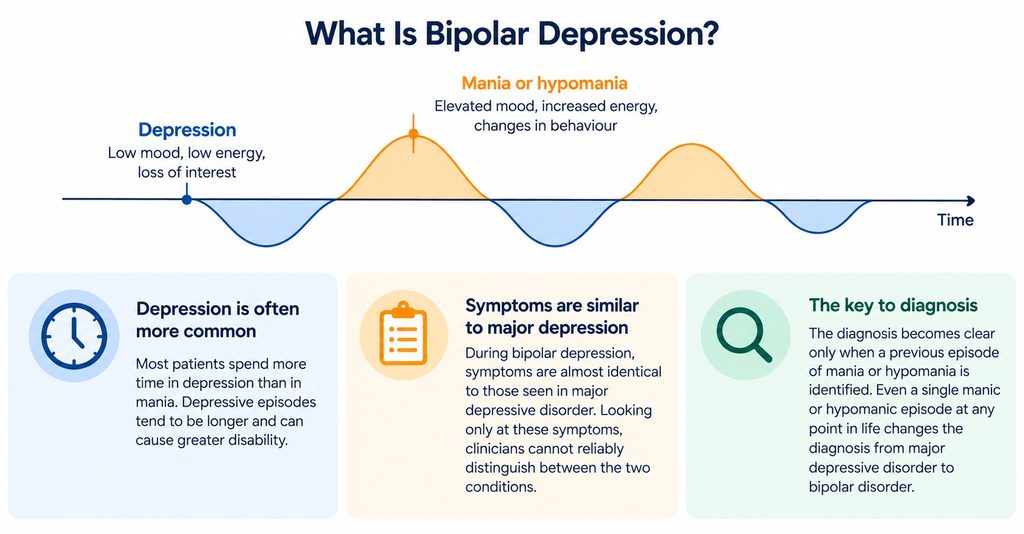
What Is Bipolar Depression?
Bipolar depression is the depressive phase of bipolar disorder, a chronic mood disorder characterised by alternating episodes of depression and periods of abnormally elevated mood, mania or hypomania.
Many people assume that bipolar disorder is mainly a disorder of excessive energy or manic behaviour. In reality, most patients spend far more time experiencing depression than mania. Depressive episodes are usually longer, more frequent, and cause greater disability than elevated mood episodes. They are also the reason why most patients seek psychiatric treatment.
During bipolar depression, symptoms are almost identical to those seen in major depressive disorder. Patients often feel persistently sad, lose interest in activities, struggle with fatigue, have difficulty concentrating, withdraw from social interactions, and experience disturbed sleep. Some develop feelings of hopelessness or suicidal thoughts. Looking only at these symptoms, even experienced clinicians cannot reliably distinguish bipolar depression from major depressive disorder.
The diagnosis becomes clear only when a previous episode of mania or hypomania is identified. Even a single manic or hypomanic episode at any point in life changes the diagnosis from major depressive disorder to bipolar disorder.
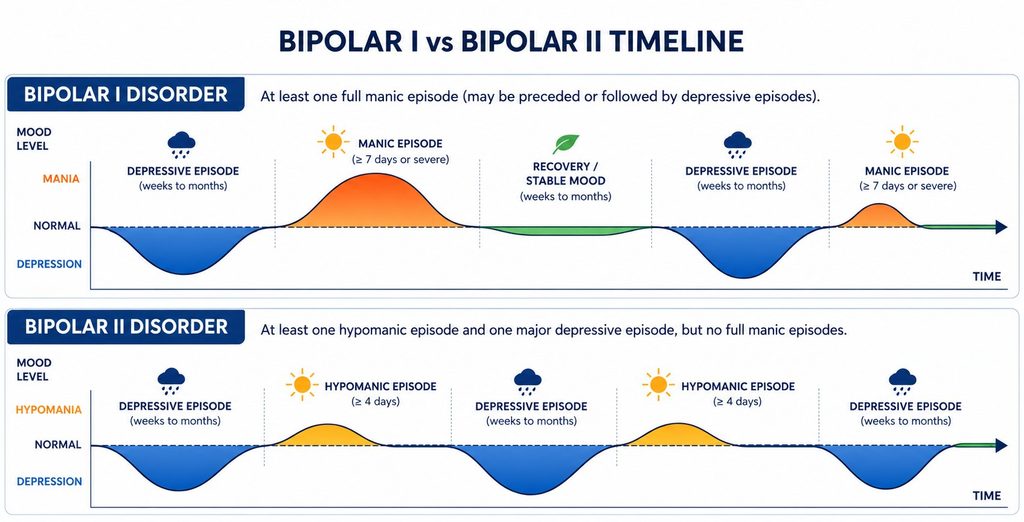
Bipolar I Disorder
Bipolar I disorder is characterised by mood swings between two extremes: mania and depression.
During mania, mood becomes abnormally elevated, expansive, or irritable, and energy levels increase dramatically. Patients often require very little sleep while continuing to feel energetic throughout the day. Thoughts race rapidly, speech becomes unusually fast, and concentration decreases because new ideas constantly interrupt previous ones. Judgement is often impaired. Some people make impulsive financial decisions, start unrealistic business projects, and engage in risky behaviour.
Depression in bipolar I disorder resembles unipolar depression, often causing profound sadness, loss of interest, fatigue, poor concentration, disturbed sleep, and feelings of hopelessness or guilt. These depressive episodes are usually longer and more frequent than manic episodes and often account for most of the illness burden. Because the symptoms of depression in bipolar I disorder are similar to those in major depressive disorder, bipolar depression is frequently misdiagnosed unless previous manic episodes are identified.
Bipolar II Disorder
Bipolar II disorder is often much more difficult to recognise because patients do not experience full mania. Instead, they develop hypomania, a milder form of mood elevation that lasts at least four days. Unlike mania, hypomania may initially seem beneficial. Individuals often feel unusually productive, creative, sociable, confident, or energetic. Friends and family may simply notice that the person appears happier or more active than usual. Because these periods rarely cause major problems, many patients never mention them during psychiatric consultations.
The depressive episodes, however, are often severe and long-lasting. As a result, bipolar II disorder is frequently mistaken for recurrent major depressive disorder. Some patients receive antidepressant treatment for years before the underlying bipolar illness is recognised.
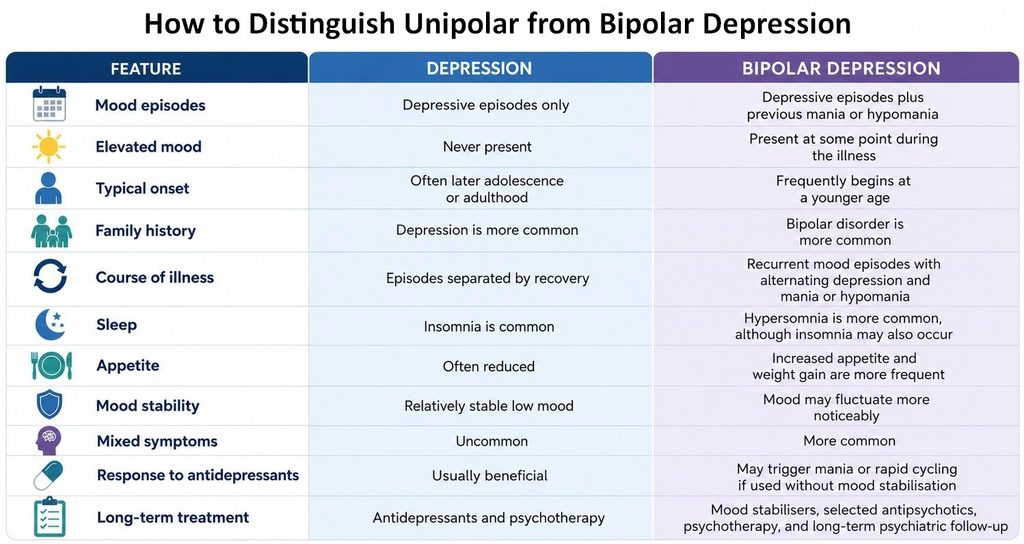
How to Distinguish Unipolar from Bipolar Depression
The simple answer is that depression looks almost the same in both illnesses. During a depressive episode, there are no obvious symptoms that immediately reveal whether the patient has major depressive disorder or bipolar disorder. Both conditions can produce low mood, emotional pain, reduced motivation, disturbed sleep, appetite changes, poor concentration, and suicidal thoughts.
Another important reason is that patients usually remember depressive episodes much more clearly than hypomanic episodes. Depression causes suffering and motivates people to seek help. Hypomania, on the other hand, may feel enjoyable or even improve work performance for a short period. Many patients therefore consider these episodes part of their normal personality rather than symptoms of an illness.
For this reason, diagnosing bipolar disorder requires more than evaluating current symptoms. The psychiatrist must carefully explore the patient’s entire psychiatric history, including previous periods of increased energy, reduced need for sleep, impulsive behaviour, and unusually elevated mood. In many cases, information from partners or close family members is also extremely valuable because they may recognise behavioural changes that the patient does not remember or consider significant.
Although depression (major depressive disorder) and bipolar depression share many symptoms, they differ in several important ways. These differences are not always obvious during a single consultation. Instead, they usually become clear when the psychiatrist carefully reviews the patient’s entire psychiatric history, including previous mood episodes, family history, and response to earlier treatments.
None of these features alone proves that a patient has bipolar disorder. However, when several are present together, the likelihood increases considerably. The diagnosis should always be based on a comprehensive psychiatric assessment rather than on a single symptom.
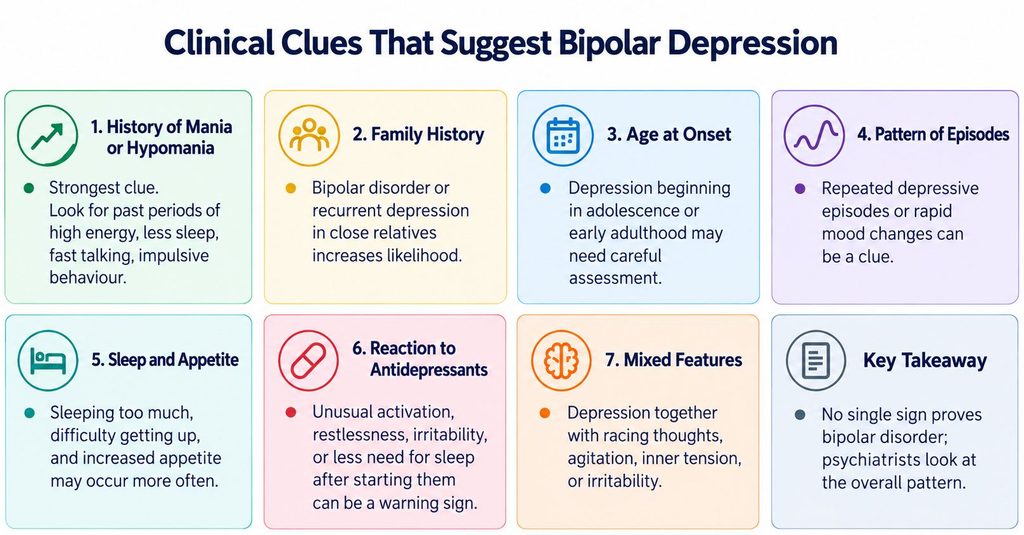
Clinical Clues That Suggest Bipolar Depression
Because depressive symptoms themselves are so similar, psychiatrists pay particular attention to characteristics that make bipolar disorder more likely. These clues do not replace a formal diagnosis, but they help determine whether further assessment is needed.
Patient’s History of Mania or Hypomania
One of the strongest indicators is a history of mania or hypomania. Many patients initially forget or overlook these episodes because they did not experience them as unpleasant. When asked specific questions, they may recall periods of unusually high energy, sleeping only a few hours each night without feeling tired, talking excessively, spending money impulsively, or starting multiple ambitious projects.
No single characteristic confirms bipolar disorder. Instead, psychiatrists combine all available information, looking for a consistent pattern that explains both current symptoms and the patient’s previous emotional experiences.
Family History of Bipolar Disorder
Family history is another important consideration. Bipolar disorder has a strong genetic component. A history of bipolar disorder, recurrent depression, psychiatric hospitalisation, or suicide among close relatives increases the likelihood that depressive symptoms may belong to the bipolar spectrum rather than representing major depressive disorder alone.
Age at Which Depression First Appeared
Another important clue is the age at which depression first appeared. Bipolar disorder often begins during adolescence or early adulthood. A patient who develops recurrent depressive episodes before the age of 25 deserves careful evaluation for possible bipolar disorder, particularly if there is also a family history of mood disorders.
Pattern of Depressive Episodes
The pattern of depressive episodes may also provide valuable information. Bipolar depression tends to recur more frequently than major depressive disorder. Patients often describe repeated episodes separated by periods of complete recovery, while others develop rapid cycling with four or more mood episodes within a year.
Sleep Patterns
Psychiatrists also ask about sleep patterns. During bipolar depression, excessive sleeping and difficulty getting out of bed are often more prominent than in major depressive disorder. Increased appetite and weight gain are also reported more frequently, although these features are not present in every patient.
Reaction to Antidepressants
A particularly important warning sign is an unexpected reaction to antidepressants. Some patients who are actually experiencing bipolar depression become unusually energetic, restless, irritable, or euphoric shortly after starting antidepressant medication. Others begin talking rapidly, sleeping very little, or engaging in impulsive behaviour. Such reactions may indicate previously unrecognised bipolar disorder or strong predestination to develop BD, rather than a simple side effect of medication.
Mixed Features
Another clue is the presence of mixed features. Instead of appearing slowed down and withdrawn, some patients feel deeply depressed while simultaneously experiencing racing thoughts, inner tension, agitation, or marked irritability. Mixed symptoms are considerably more common in bipolar disorder than in major depressive disorder and require particular attention because they are associated with a higher risk of suicide and often respond poorly to antidepressant monotherapy.

Why Bipolar Disorder Is Misdiagnosed
One of the greatest challenges in psychiatry is that patients with bipolar disorder usually seek help because of depression, not because of mania.
During a depressive episode, patients experience emotional suffering, loss of functioning, and hopelessness, which naturally motivate them to consult a psychiatrist. In contrast, hypomanic episodes are often perceived as positive experiences. Individuals may feel unusually confident, productive, sociable, or creative. Because these periods seem beneficial, they are rarely mentioned unless the psychiatrist asks specific questions.
This explains why many people receive a diagnosis of major depressive disorder during their first psychiatric consultation, even though they actually have bipolar disorder. Studies have shown that bipolar disorder, particularly bipolar II disorder, is frequently underdiagnosed, and diagnosis may be delayed for many years.
Family members often recognise manic or hypomanic behaviour more readily than the patient. During elevated mood, insight is commonly reduced. Patients may genuinely believe they are simply functioning exceptionally well, while partners or relatives observe dramatic personality changes, impulsive decisions, excessive spending, or unusually reduced sleep.
For this reason, psychiatrists frequently encourage patients to involve a close family member or partner during the diagnostic assessment. Information from relatives can provide valuable details about previous mood episodes that might otherwise remain unnoticed.
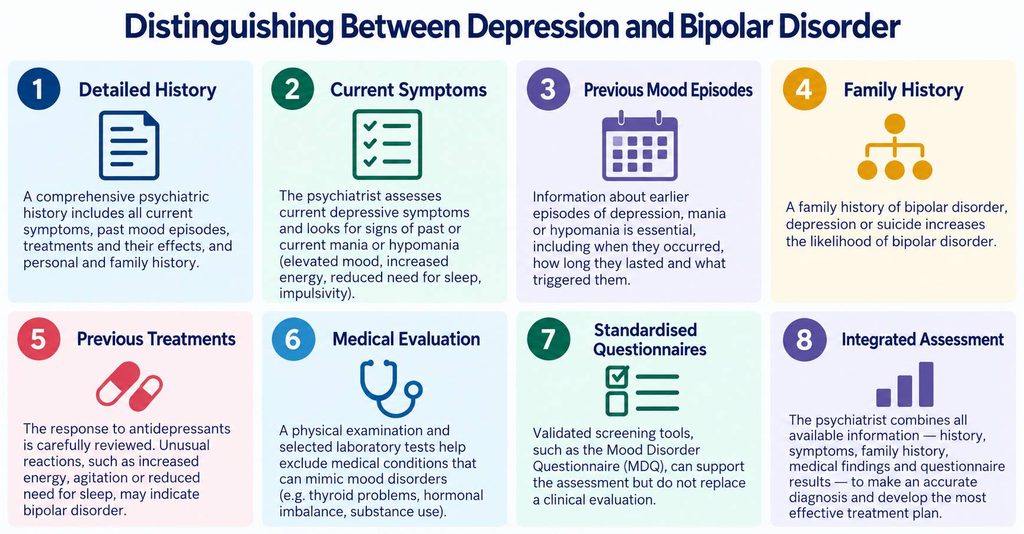
Distinguishing Between Depression and Bipolar Disorder
There is no blood test, brain scan, or laboratory investigation that can reliably distinguish major depressive disorder from bipolar disorder. The diagnosis is made through a comprehensive psychiatric assessment that evaluates not only the patient’s current symptoms but also their entire psychiatric history.
Ultimately, diagnosing bipolar disorder resembles assembling a puzzle. No single symptom provides the answer. Instead, the psychiatrist combines information about current symptoms, previous mood episodes, sleep patterns, family history, treatment response, and longitudinal course to reach the most accurate diagnosis possible.
First Consultation
For many patients, the diagnosis cannot be established during the first consultation alone. Mood disorders develop over time, and understanding their pattern often requires careful exploration of previous episodes, treatment responses, and changes in behaviour throughout life. An experienced psychiatrist looks beyond the current depressive symptoms and tries to understand the illness as a whole.
Clinical Interview
One of the first questions concerns previous episodes of unusually elevated mood. Patients are asked whether they have ever gone through periods when they needed far less sleep than usual while still feeling energetic. They may be asked whether they became unusually talkative, started numerous projects at the same time, spent excessive amounts of money, became more socially active than usual, or felt exceptionally confident or powerful.
Many patients initially answer “no” because they remember these periods as productive rather than abnormal. Only after discussing specific examples do they recognise that these episodes may have represented hypomania rather than simply a “good mood”. This is one of the reasons why bipolar disorder can remain undiagnosed for many years.
Receiving the Correct Diagnosis
For many patients, receiving the correct diagnosis is an important turning point. After years of repeated depressive episodes and only partly effective treatments, understanding that depression is part of bipolar disorder allows a more effective treatment plan to be developed. With appropriate medication, psychotherapy, and regular psychiatric care, many people achieve long-term mood stability and lead productive, fulfilling lives.
Investigating Previous Depressive Episodes
The psychiatrist also carefully reviews the course of previous depressive episodes. Questions focus on when the first episode occurred, how often depression has returned, how long individual episodes lasted, and whether there were symptom-free periods in between. Depression beginning during adolescence or early adulthood, particularly when episodes recur frequently, raises suspicion for bipolar disorder.
Reviewing Family History
Family history provides another important clue. Bipolar disorder has a strong genetic component. A history of bipolar disorder, recurrent depression, suicide, or psychiatric hospitalisation among first-degree relatives increases the likelihood that depressive symptoms belong to the bipolar spectrum rather than representing isolated major depressive disorder. Although family history alone cannot establish the diagnosis, it contributes valuable information to the overall assessment.
Evaluation of Previous Treatments
Another essential part of the evaluation is reviewing previous treatments. Patients who have experienced unusually increased energy, agitation, irritability, or reduced sleep shortly after starting an antidepressant may actually have underlying bipolar disorder. Such reactions are not diagnostic on their own, but they warrant further assessment before antidepressant treatment is continued.
Interview of Family Members
Whenever possible, psychiatrists also obtain information from family members. This is particularly valuable because patients often have limited insight during manic or hypomanic episodes. Relatives may describe periods of impulsive behaviour, excessive confidence, dramatic personality changes, or reduced need for sleep that the patient either forgot or never considered abnormal.
Use of Screening Questionnaires
Several validated screening questionnaires, such as the Mood Disorder Questionnaire (MDQ) or the Bipolar Spectrum Diagnostic Scale (BSDS), may support the assessment. These questionnaires do not establish the diagnosis by themselves, but they can help identify patients who require a more detailed psychiatric evaluation.
Excluding Influence of Medical Conditions
Before confirming either diagnosis, the psychiatrist also excludes medical conditions that may produce similar symptoms. Depending on the patient’s history, this may include a physical examination, blood tests, thyroid function tests, or other investigations when clinically indicated. Alcohol and substance use are also assessed because they can both mimic and worsen mood disorders.
Why the Correct Diagnosis Matters
Confusing bipolar depression with major depressive disorder can have important consequences because the treatment approaches are fundamentally different. Although both conditions involve depressive symptoms, they arise from different underlying mood disorders and therefore require different long-term management.

Medication of Depressive Episode of Bipolar Disorder
In bipolar disorder, however, antidepressants require much greater caution. When prescribed without a mood stabiliser, they may trigger mania or hypomania in susceptible individuals. In some patients they can also increase the frequency of mood episodes, contribute to rapid cycling, or fail to adequately control bipolar depression. This is why antidepressant monotherapy is generally not considered the first-line treatment for bipolar disorder.
Instead, the foundation of bipolar disorder treatment consists of mood stabilisers and selected atypical antipsychotic medications. These medications aim not only to treat the current depressive episode but also to prevent future episodes of both depression and mania. Depending on the individual patient, treatment may include medications such as lithium, lamotrigine, quetiapine, or other evidence-based therapies selected according to international treatment guidelines.
Differences in Use of Psychotherapy
Psychotherapy also plays an important role in both disorders, although its goals differ slightly. In major depressive disorder, therapy often focuses on modifying negative thought patterns, improving coping strategies, and reducing the risk of relapse. In bipolar disorder, psychotherapy additionally helps patients recognise early warning signs of mania or depression, maintain regular sleep routines, improve adherence to medication, and develop strategies to prevent future mood episodes.
Long-Term Psychiatric Monitoring
Long-term psychiatric follow-up is particularly important for bipolar disorder because it is usually a lifelong condition. Even after symptoms have resolved completely, the underlying vulnerability remains. Regular follow-up appointments allow treatment to be adjusted, side effects to be monitored, and early signs of relapse to be recognised before a full mood episode develops.

When Should You See a Psychiatrist?
Many people believe that depression is always the same illness. As a result, they may not realise that recurring depressive episodes, especially when accompanied by periods of unusually high energy or reduced need for sleep, could indicate bipolar disorder rather than major depressive disorder.
A psychiatric assessment is particularly important if depression begins at a young age, returns repeatedly despite treatment, or there is a family history of bipolar disorder. It is also advisable when antidepressants have provided little benefit or have caused unusual reactions such as excessive energy, irritability, restlessness, or decreased need for sleep.
Patients who notice dramatic changes in mood, alternating between prolonged periods of depression and episodes of feeling unusually energetic or impulsive, should also seek specialist evaluation. These mood changes are not always recognised as symptoms of bipolar disorder, particularly when elevated moods feel pleasant or productive
Anyone experiencing suicidal thoughts, psychotic symptoms, severe impairment in daily functioning, or rapid changes in mood should seek urgent psychiatric care. Early diagnosis allows treatment to begin before further episodes develop and reduces the risk of long-term complications.
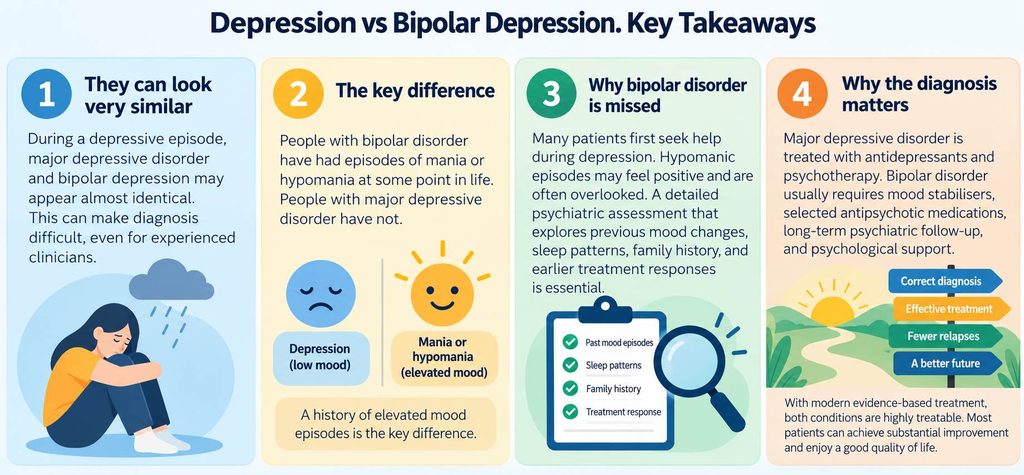
Depression vs Bipolar Depression. Key Takeaways
Although depression and bipolar depression share many symptoms, they are different illnesses that require different treatment approaches. During a depressive episode, they can appear almost identical, making diagnosis challenging even for experienced clinicians. The critical distinction is that people with bipolar disorder have experienced episodes of mania or hypomania at some point during their lives, whereas those with major depressive disorder have not.
Because many patients with bipolar disorder first seek help during depression, hypomanic episodes are often overlooked. A detailed psychiatric assessment that explores previous mood changes, sleep patterns, family history, and earlier treatment responses is therefore essential before making the diagnosis.
The correct diagnosis has a direct impact on treatment. Major depressive disorder is commonly treated with antidepressants and psychotherapy, while bipolar disorder usually requires mood stabilisers, selected antipsychotic medications, long-term psychiatric follow-up, and psychological support. Identifying bipolar disorder early helps prevent inappropriate treatment, reduces the risk of relapse, and significantly improves long-term outcomes.
With modern evidence-based treatment, both major depressive disorder and bipolar disorder are highly treatable. Most patients can achieve substantial symptom improvement, return to work, maintain healthy relationships, and enjoy a good quality of life.
Concerned About Your Diagnosis?
If you have experienced recurrent depression, episodes of unusually high energy, or antidepressants have not worked as expected, a comprehensive psychiatric assessment may help clarify the diagnosis. Correctly distinguishing depression from bipolar disorder is the first step towards safe and effective treatment.
At CHMC Dubai, Dr. Gregor Kowal, German Board-Certified Consultant Psychiatrist and Psychotherapist, performs detailed psychiatric assessments that evaluate not only current symptoms but also your previous mood episodes, sleep patterns, family history, treatment response, and overall course of illness. This careful approach helps ensure an accurate diagnosis and an individualised treatment plan based on current international guidelines.

FAQs About Depression vs Bipolar Depression
Can bipolar depression feel exactly like monopolar depression?
Yes. During a depressive episode, bipolar disorder can produce almost the same symptoms as major depressive disorder, including persistent sadness, fatigue, loss of interest, poor concentration, sleep disturbances, and feelings of hopelessness. The difference becomes apparent only when a history of mania or hypomania is identified.
What is the main difference between depression and bipolar depression?
The defining difference is the presence of manic or hypomanic episodes. People with depression experience episodes only, whereas people with bipolar disorder alternate between depression and periods of elevated mood, increased energy, or irritability.
Why is bipolar disorder often mistaken for depression?
Most patients seek medical help during depressive episodes because these cause the greatest distress. Hypomanic episodes may feel enjoyable or productive and are therefore often forgotten or not considered symptoms of an illness. Without a detailed psychiatric history, bipolar disorder may be misdiagnosed as depression.
Can antidepressants make bipolar disorder worse?
They can. In some patients, antidepressants prescribed without a mood stabiliser may trigger mania, hypomania, or more frequent mood episodes. This is one reason why psychiatrists always assess for bipolar disorder before starting antidepressant treatment.
Is bipolar depression more severe than major depression?
Both conditions can cause severe disability. However, bipolar disorder is usually a lifelong illness with recurrent mood episodes, making long-term treatment and monitoring particularly important. The depressive phase of bipolar disorder often accounts for most of the illness burden.
Can bipolar disorder develop later in life?
Although bipolar disorder most commonly begins during adolescence or early adulthood, it can occasionally develop later. Every new episode of depression should be assessed individually, particularly if symptoms or treatment responses are unusual.
How is bipolar disorder diagnosed?
Diagnosis is based on a comprehensive psychiatric assessment. The psychiatrist reviews current symptoms, previous mood episodes, family history, sleeping patterns, earlier treatments, and, when appropriate, information from close relatives. There is currently no laboratory test that confirms bipolar disorder.
Can psychotherapy help both conditions?
Yes. Psychotherapy is an important part of treatment for both depression and bipolar disorder. It helps patients understand their illness, develop healthy coping strategies, recognise early warning signs of relapse, and improve long-term recovery.
Does everyone with bipolar disorder experience severe mania?
No. Patients with Bipolar II disorder experience hypomania, which is milder than mania and may not cause major impairment. Because hypomania often feels positive, many patients do not recognise it as a symptom until they undergo a detailed psychiatric assessment.
Can people with bipolar disorder live normal lives?
Absolutely. With an accurate diagnosis, appropriate medication, psychotherapy, and regular psychiatric follow-up, many people with bipolar disorder remain emotionally stable for years, maintain successful careers, enjoy healthy relationships, and lead active, fulfilling lives.
Can depression become bipolar disorder?
Depression does not “turn into” bipolar disorder. In many patients, the first episode of bipolar disorder is depression. The diagnosis changes only when mania or hypomania later becomes apparent.
Read More About Bipolar Disorder
- Treatment for Bipolar Disorder
- Symptoms of Bipolar Disorder
- Diagnosis of Bipolar Disorder
- Self-Test for Bipolar Disorder
- Psychiatrist for Bipolar Disorder
- When is Hospital Admission Necessery for BD
- Bipolar Disorder in Pregnancy
- Medication for Bipolar Disorder
- Psychotherapy for Bipolar Disorder
- Causes of Bipolar Disorder
- Bipolar I vs Bipolar II Disorder
- What is Rapid Cycling?
- Bipolar Disorder and Sleep
- Living with Bipolar Disorder
- Relationships, Family, Everyday Life with BD
- Long Term Recovery & Quality of Life with BD
- What is Mania and Hypomania?
- Cyclothymic Disorder
- History of Bipolar Disorder
- CANMAT Guidelines for Bipolar Disorder
- Mood Stabilizers for Bipolar Disorder
- Lithium for Bipolar Disorder

