

ADHD and Borderline Personality Disorder (BPD) are distinct psychiatric conditions that can share several symptoms, including impulsivity, emotional dysregulation and difficulties in interpersonal relationships. Because these similarities can be pronounced, distinguishing ADHD from BPD is sometimes challenging, particularly in adults whose symptoms were not recognised earlier in life.
The most important difference lies in the overall pattern, developmental history and psychological context of the symptoms. ADHD is a neurodevelopmental disorder characterised by persistent difficulties with attention regulation and/or hyperactivity-impulsivity, often accompanied by executive dysfunction. BPD, in contrast, involves a pervasive pattern of instability in emotional regulation, interpersonal relationships, self-image and behaviour.
Understanding the differences between ADHD and BPD is important because the conditions require different therapeutic approaches and may also occur together. An accurate psychiatric assessment must therefore consider more than isolated symptoms, examining how difficulties develop, what triggers them and how they affect everyday functioning.
For ADHD vs BPD assessment, contact our consultant psychiatrist Dr. Kowal
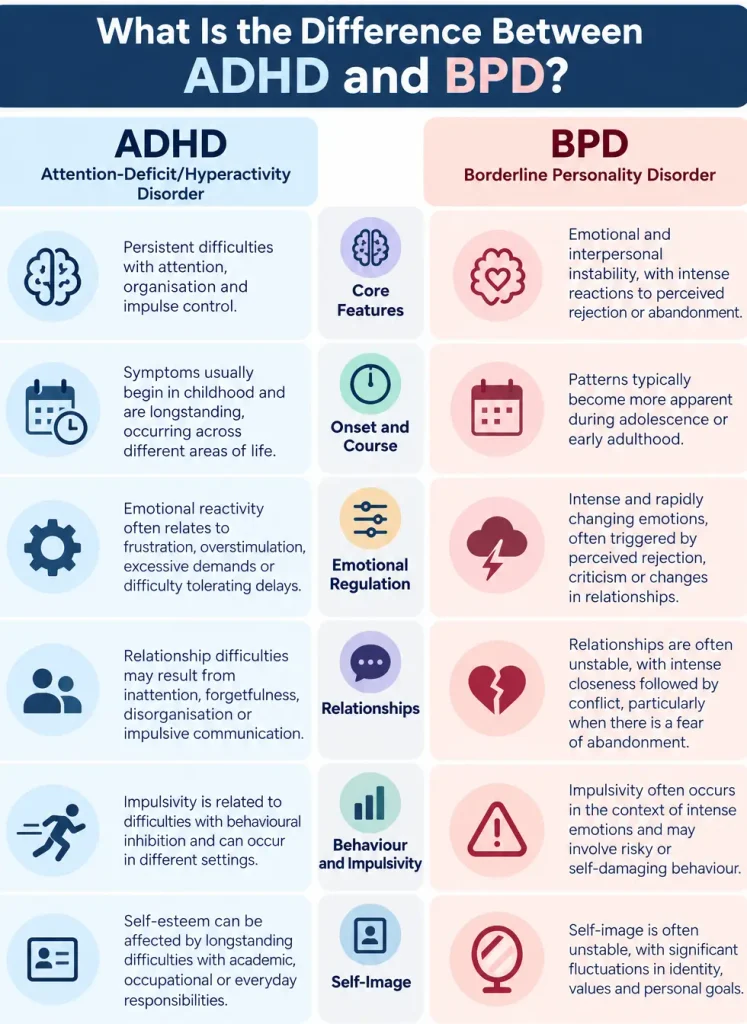
What Is the Difference Between ADHD and BPD?
Although ADHD and BPD can produce similar outward behaviours, their characteristic clinical patterns differ. In ADHD, difficulties with attention, organisation and impulse control are usually longstanding and occur across different areas of life. A person may frequently lose concentration, forget appointments, interrupt conversations, act without sufficient planning or struggle to complete routine responsibilities. Emotional reactivity can also occur, particularly in situations involving frustration, excessive demands or difficulty tolerating delays.
In Borderline Personality Disorder, emotional and interpersonal instability are central features. Patients may experience intense reactions to perceived rejection or abandonment, unstable relationships, disturbances in self-image and difficulty regulating powerful emotional states. Impulsive behaviour may occur in the context of these experiences and can be accompanied by significant distress.
Neither impulsivity nor emotional instability alone can reliably distinguish ADHD from BPD. The psychiatrist must evaluate the persistence of symptoms, their relationship to interpersonal events, the presence of childhood ADHD symptoms and the wider pattern of psychological functioning.
Emotional Dysregulation in ADHD vs BPD
Emotional dysregulation is one of the most important areas of overlap between ADHD and Borderline Personality Disorder. Both conditions can involve intense emotional reactions, irritability and difficulties managing distress, but the circumstances and associated psychological experiences may differ.
In ADHD, emotional reactions are often associated with frustration, overstimulation, interruption, waiting or difficulties controlling immediate responses. A person may become rapidly irritated when plans change unexpectedly or when a demanding task becomes overwhelming. Emotional reactions can be intense but may subside once the triggering situation has passed. However, emotional dysregulation is not a formal core diagnostic criterion of ADHD, and its presentation varies considerably between individuals.
In BPD, emotional instability frequently occurs within a broader pattern of interpersonal sensitivity and difficulties maintaining a stable sense of self. Perceived rejection, criticism, abandonment or changes in an important relationship may provoke intense distress, anger or anxiety. These reactions can be accompanied by abrupt changes in the person’s perception of themselves or others, sometimes contributing to significant relationship conflict.
These distinctions are useful but not absolute. Individuals with ADHD can also experience rejection sensitivity and prolonged emotional distress, while people with BPD may react strongly to situations unrelated to relationships. The diagnostic significance lies in the wider symptom pattern rather than the intensity or duration of an individual emotional reaction.
For a more detailed discussion of emotional control in ADHD, see Emotional Dysregulation in ADHD.
Impulsivity in ADHD vs Borderline Personality Disorder
Impulsivity is a core diagnostic feature of ADHD and can also be prominent in BPD. The distinction often concerns the situations in which impulsive behaviour occurs and the psychological factors associated with it.
In ADHD, impulsivity is closely related to difficulties with behavioural inhibition. A person may interrupt conversations, answer questions prematurely, become impatient while waiting or make decisions without sufficient consideration of the consequences. These behaviours are often longstanding and occur in different settings, including work, education and everyday social interactions.
In BPD, impulsive behaviour may be more closely connected with intense emotional distress or interpersonal difficulties. Examples can include reckless spending, substance misuse or other potentially self-damaging behaviours, particularly during periods of emotional instability. However, these behaviours are not exclusive to BPD, and similar problems can occur in ADHD or other psychiatric conditions.
The psychiatrist therefore examines whether impulsivity forms part of a persistent neurodevelopmental pattern or occurs within a broader constellation of emotional, interpersonal and identity-related difficulties. Both mechanisms may also be present when ADHD and BPD coexist.
Relationships and Self-Image in ADHD vs BPD
Both disorders can significantly affect relationships and self-esteem, but the underlying difficulties are not necessarily the same. Understanding how interpersonal problems develop and how individuals perceive themselves can provide important diagnostic information.
Relationship Difficulties in ADHD vs BPD
In ADHD, relationship problems may arise from forgetfulness, distractibility, disorganisation, impulsive communication or emotional reactivity. A person may unintentionally interrupt their partner, overlook commitments or struggle to manage shared responsibilities. These behaviours can be interpreted as indifference or unreliability, even when they result primarily from difficulties with attention and executive functioning.
In BPD, relationship difficulties are more characteristically associated with instability in attachment, intense sensitivity to perceived rejection or abandonment and fluctuations in how other people are perceived. Relationships may alternate between periods of strong emotional closeness and significant conflict, particularly when the person experiences insecurity or fears losing an important relationship.
Although these patterns can help differentiate the disorders, relationship difficulties alone are not sufficient for diagnosis. Attachment history, emotional regulation, behavioural patterns and the presence of other psychiatric symptoms must also be considered.
Self-Image and Identity in ADHD vs BPD
Adults with ADHD may develop negative beliefs about themselves following years of difficulties with academic performance, organisation, deadlines or everyday responsibilities. Repeated criticism and unsuccessful attempts to meet expectations can contribute to low self-esteem, frustration and feelings of inadequacy.
In BPD, disturbances of identity can extend beyond negative self-evaluation. The individual may experience marked instability in their sense of self, personal goals, values or perceptions of who they are. These changes may be closely connected with emotional states and interpersonal experiences.
Low self-esteem resulting from longstanding ADHD-related difficulties should not automatically be interpreted as evidence of a personality disorder. The distinction requires an assessment of whether the problem primarily concerns negative self-evaluation or a broader instability of identity.
Attention and Executive Dysfunction in ADHD vs BPD
Persistent difficulties with attention and executive functioning are central to the clinical presentation of ADHD. Adults may struggle with planning, prioritising responsibilities, working memory, time management, organising complex tasks and sustaining concentration during activities that provide little immediate stimulation. These difficulties typically occur across multiple situations and are not limited to periods of emotional distress.
People with BPD can also experience impaired concentration, especially during intense emotional arousal, anxiety, interpersonal conflict or dissociative experiences. However, attentional difficulties are not among the defining diagnostic features of BPD in the same way that inattention is central to ADHD.
A clinically useful distinction concerns whether organisational and attentional difficulties are longstanding and evident independently of emotional crises or primarily emerge during periods of psychological distress. Nevertheless, both conditions can affect cognitive functioning, and the presence of executive dysfunction does not exclude BPD.
Childhood History: A Key Difference Between ADHD and BPD
Developmental history is particularly important when distinguishing ADHD from Borderline Personality Disorder. ADHD is classified as a neurodevelopmental disorder, and its diagnostic criteria require evidence that several symptoms were present before the age of 12. Although ADHD may not be recognised until adulthood, earlier difficulties with attention, activity level, organisation or impulse control should generally be identifiable retrospectively.
Some adults have limited recollection of their childhood behaviour, particularly when their difficulties were less disruptive or were compensated for by a structured environment. School reports, descriptions from parents or family members and information about academic and social functioning may therefore help establish whether characteristic symptoms were present during development.
BPD is characterised by a pattern of personality functioning and interpersonal difficulties that generally becomes more apparent during adolescence or early adulthood. However, emotional and interpersonal vulnerabilities may also have earlier developmental origins, so age of onset alone cannot reliably separate the conditions.
The central question is whether symptoms consistent with ADHD were already present in childhood and whether they continued across different stages of life. A clear developmental history can help distinguish persistent attentional and behavioural difficulties from emotional or interpersonal patterns that become prominent later.
Can ADHD and BPD Occur Together?
ADHD and Borderline Personality Disorder can coexist, and the presence of one diagnosis does not exclude the other. When both conditions are present, difficulties with attention, impulse control and organisation may interact with emotional instability, interpersonal sensitivity and problems regulating behaviour.
This combination can complicate clinical assessment because symptoms from one disorder may intensify difficulties associated with the other. For example, impulsive communication or forgetfulness related to ADHD may contribute to relationship conflict, while emotional distress associated with BPD may further impair concentration and executive functioning.
A comprehensive assessment must therefore determine which symptoms are attributable to ADHD, which form part of BPD and whether other psychiatric conditions contribute to the clinical presentation. Recognising both disorders is important because treatment directed exclusively toward one condition may leave significant difficulties insufficiently addressed.
ADHD vs BPD in Women: Diagnostic Challenges
Differentiating ADHD from BPD can be particularly challenging in women, although diagnostic confusion is not limited to women. Some women with ADHD are diagnosed relatively late because their childhood presentation may have involved predominantly inattentive symptoms rather than conspicuous hyperactivity or disruptive behaviour.
By adulthood, longstanding difficulties with organisation, impulsivity and emotional regulation may have contributed to anxiety, depression, relationship conflict or reduced self-esteem. If the assessment focuses primarily on emotional instability without exploring developmental history and executive functioning, ADHD may be overlooked.
Conversely, a diagnosis of ADHD should not automatically be used to explain every emotional or interpersonal difficulty. Some individuals may fulfil diagnostic criteria for BPD or another psychiatric disorder in addition to ADHD, while others may have symptoms better explained by a different condition altogether.
Misdiagnosis can occur in either direction. The psychiatrist must distinguish between overlapping symptoms and evaluate the full clinical picture rather than relying on isolated behaviours, assumptions about gender or the results of screening questionnaires.
How Are ADHD and BPD Diagnosed?
There is no blood test, brain scan or single psychological questionnaire that can reliably distinguish ADHD from Borderline Personality Disorder. Diagnosis depends on a comprehensive clinical assessment examining current symptoms, developmental history, functional impairment and the overall pattern of psychological difficulties.
When ADHD is suspected, the psychiatrist evaluates symptoms of inattention and hyperactivity-impulsivity, evidence of childhood onset and their effects across different areas of life. Information from school records or people familiar with the patient’s earlier development may be helpful when available. The assessment also considers conditions that can produce similar symptoms, including mood, anxiety, trauma-related and sleep disorders.
When BPD is suspected, particular attention is given to longstanding patterns of emotional regulation, interpersonal relationships, self-image and impulsive behaviour. The psychiatrist considers whether these difficulties form a persistent pattern consistent with a personality disorder and whether other psychiatric conditions provide alternative or additional explanations.
Accurate differential diagnosis is important because ADHD and BPD have different treatment priorities. ADHD treatment may involve medication, psychoeducation and ADHD-focused psychological interventions, while structured psychotherapy is the principal treatment approach for BPD. When both conditions coexist, treatment planning must address the difficulties associated with each disorder.
For a detailed explanation of the assessment process, see ADHD Diagnosis in Dubai.

ADHD vs Borderline Personality Disorder: Key Takeaways
ADHD and Borderline Personality Disorder share symptoms such as impulsivity, emotional dysregulation and relationship difficulties, but they differ in their characteristic developmental course and overall clinical presentation. ADHD primarily involves persistent difficulties with attention regulation and/or hyperactivity-impulsivity beginning in childhood, often accompanied by executive dysfunction. BPD is characterised by a pervasive pattern of emotional, interpersonal and self-image instability.
Distinguishing these conditions requires consideration of the complete clinical picture rather than any individual symptom. Childhood history, the persistence of attentional difficulties, the context of emotional reactions, relationship patterns and stability of self-image are particularly informative. ADHD and BPD may also coexist, making comprehensive psychiatric assessment essential when the diagnosis is uncertain.
At CHMC German Clinic for Psychiatry and Psychology in Dubai, Dr. Gregor Kowal, German Board-Certified Consultant Psychiatrist and Psychotherapist, provides specialist assessment of ADHD and psychiatric conditions with overlapping symptoms. The evaluation considers developmental history, psychiatric symptoms and individual functioning to establish an accurate diagnosis and guide appropriate treatment.
Patients seeking a specialist assessment can learn more about ADHD treatment in Dubai or contact CHMC to arrange a consultation.

Frequently Asked Questions About ADHD vs BPD
Can ADHD be mistaken for Borderline Personality Disorder?
Yes. ADHD can sometimes be mistaken for BPD when emotional reactivity, impulsivity and relationship difficulties dominate the clinical presentation. A careful assessment of childhood symptoms, attention regulation, executive functioning and the broader interpersonal pattern helps distinguish the conditions and identify possible comorbidity.
What is the main difference between ADHD and BPD?
ADHD is a neurodevelopmental disorder characterised by persistent symptoms of inattention and/or hyperactivity-impulsivity beginning in childhood. BPD involves a pervasive pattern of difficulties with emotional regulation, interpersonal relationships, self-image and impulsive behaviour. Both conditions can share symptoms, so diagnosis requires evaluation of the overall clinical pattern.
Can someone have ADHD and BPD at the same time?
Yes. ADHD and BPD can occur together, and their symptoms may interact. A person may experience longstanding attention and executive-function difficulties associated with ADHD alongside emotional and interpersonal instability characteristic of BPD. Both conditions need to be considered during assessment and treatment planning.
How can a psychiatrist distinguish ADHD from BPD?
The psychiatrist examines developmental history, symptom persistence, emotional triggers, executive functioning, relationships and self-image. Evidence of ADHD symptoms during childhood is particularly important, while patterns of emotional and interpersonal instability help inform assessment for BPD. No single symptom or questionnaire can reliably distinguish the disorders.
Is emotional dysregulation always a sign of BPD?
Emotional dysregulation can occur in ADHD, depression, anxiety disorders, trauma-related conditions and other psychiatric disorders. Although it is a characteristic feature of BPD, emotional dysregulation alone is insufficient to establish the diagnosis. Its clinical significance depends on the wider pattern of symptoms and associated difficulties.


